News Flash 679: Weekly Snapshot of Public Health Challenges

News Flash Links, as part of the research project PEAH (Policies for Equitable Access to Health), aim to focus on the latest challenges by trade and governments rules to equitable access to health in resource-limited settings

Mauve stinger (Pelagia noctiluca)

News Flash 679

Weekly Snapshot of Public Health Challenges


Global civil society warns IMF against a return to deeper austerity

Webinar registration: IFIC Scotland Webinar: Role of Compassionate Communities in Integrated Palliative Care Oct 1, 2026

Urgent Sign-On: EU must drop TRIPS-plus demands from Malaysia–EU FTA (Deadline: Friday, 18 September 2026)

ICIC 27 Tallinn: call for abstracts now open

Is the global humanitarian system collapsing?

AI, Health Dashboards and the Future  by Philip J. Gover 

King Charles to host AI executives as threat fears mount

AI, Gender Equality, and Self-Healing

HRR834. SOWING FOOD SOVEREIGNTY IS WHAT WILL ENSURE FOOD SECURITY PERIOD

Interview: Veena S Rao, ACPN Director, India  by Daniele Dionisio 

WHO and Commonwealth Secretariat renew partnership to strengthen health systems and advance universal health coverage

New DNDi report: Implementing Article 9.5 of the WHO Pandemic Agreement – building on current policy and practice for publicly funded R&D

Drug discovery explained: Moonshot: open science to prepare for pandemics?

Interview with Elizabeth Kaplan on changes to the U.S. Preventive Services Task Force and the importance of evidence-based recommendations for preventive services

What can digital PFM deliver for the health sector?

NGO chief sees ‘hypocrisy’ in Afghan women’s rights calls amid aid cuts

When Harm Hides in Hospital: Messaging and the Medicalisation of Female Genital Mutilation

Childbirth abuse is rife. So why don’t we see it?

Too Old and A Woman: Systemic Age and Gender Discrimination Against Women at Work in South Korea

Europe is failing its legal and moral obligation to save lives at sea

Yemen: Renewed fighting puts pressure on the health system and increases people’s humanitarian needs

Bundibugyo Virus Outbreak Shows Signs of Containment in Northeastern DRC – Still Expanding Elsewhere

Ebola outbreak is DRC’s worst. Where is the vaccine?

Global health ethics in international collaborative research during policy transition: what can we learn from the proposed newborn hepatitis B vaccine trial in Guinea-Bissau?

New Cost Estimate Tool to Aid U.S. Measles Outbreak Response

Chile becomes first country in South America validated for eliminating dog-transmitted rabies as a public health problem

Feasibility of paediatric schistosomiasis prevention with praziquantel, Madagascar

Food Shortages and Cholera Deepen Sudan’s Humanitarian Crisis

Will There Be an African Energy Revolution? That Depends on Who Funds What

Investment in Irrigation Systems Is Vital in Preparing for the Next Climate Shock


AI, Health Dashboards and the Future

IN A NUTSHELL
Author's note

This article asks whether an AI-driven health score can turn information about long-term risk into behaviour that actually changes. It begins with an experiment: an AI tool built to estimate life expectancy, and what happened when the apparent precision of its output was tested. The number was removed.

What follows examines feedback and its limits, drawing on the evidence for in-car and roadside driver feedback, personalised risk communication including genetic risk, the NHS heart age test, Geoffrey Rose's distinction between sick individuals and sick populations, the nudge literature after correction for publication bias, and the arrival of consumer-facing continuous monitoring.

The central argument is that measurement is most useful when it is immediate, attached to an achievable action, and embedded in a cycle of feedback, incentive and repetition. The article argues against false precision, and against assuming that information alone changes what people do, while recognising that modest effects can still produce substantial benefit at scale. It concludes that the future of health dashboards lies not in producing ever more authoritative numbers, but in helping people see what they can change, act on it, watch what happens, and keep going

By Philip J. Gover, BA, MA, MPH, FCMI, FRSPH

Cooperation Works

Cambodia

Comments welcome 

For partnership opportunities: philip.gover@cooperation.works

 By the same Author on PEAH: see HERE

AI, Health Dashboards and the Future

I Built An AI Tool To Predict How Long You Will Live, Then Checked Whether The Idea Works


There is a small piece of engineering in most cars that changed how people drive, without ever saying a word to them. It is the little screen that shows how much fuel you are using, right now, as you drive.

Before it existed, everyone already knew that heavy acceleration burns more fuel. It was not a secret. It was on the news whenever fuel prices rose, and in the cost of filling the tank each month. Almost nobody changed their driving habits. Then the number appeared on the dashboard, moving as you drove, and people began to ease off. They had not learned anything new. The cost had simply stopped being an idea and become something they could watch while their foot was on the pedal.

That gap, between knowing a thing and feeling it at the moment you act, is where most good advice dies. I have come to call it the dashboard problem. Health looks like the worst case of it. Very few people lack information. Most adults can recite the list: move more, drink less, sleep properly, check your blood pressure, do not smoke, do not sit still all day. We are not failing a test of knowledge. We are failing at attention.

The feedback in health arrives 20 or 30 years late, which is to say it does not arrive at all. You cannot feel your arteries. There is no pedal to lift, and no gauge on the dashboard for that. The obvious move, and I made it, is to build the gauge.

What I Built

I spent a while building a prompt: a set of instructions you paste into any AI LLM assistant. It asks 23 questions, one at a time, the way a good doctor asks them rather than the way a form asks them. Your age. Whether you smoke. How much you drink. How you sleep. The state of your gums. Whether your father died at 61, and of what. Whether there is anyone you could telephone at three in the morning. At the end, numbers. Your likely age at death, with a range around it, and a table showing how that range if you changed the two or three things most worth changing. Know your number. It moved is a good hook, and I liked it very much. Then I ran it several times with the same answers, and watched the number move by years. That is a story, not a test, and I will not dress it up as evidence.

What it did was send me looking further and looking properly: first at what the tool was doing, then, less comfortably, at whether the whole idea works.

The Number Is Not Real

The obvious complaint is that an AI large language model is not an Actuary. It has no lifetables inside it. When it says “79, with a 95% range of 71 to 86”, It has not calculated anything. It has written a sentence of the shape that such sentences usually take, and filled it with digits that feel about right. Asked directly, it says as much itself. However that could be fixed, by connecting a real published risk model and doing the arithmetic honestly.

Yet the deeper problem still survives the fix. How long any one person lives varies enormously, and no questionnaire reaches most of that variation. Ask all 23 questions, measure every answer perfectly, and the remaining spread is still far too wide to plan against. A truthful range is not a dashboard. The precision that makes the tool exciting is exactly the precision that does not exist.

Of what I know about the human condition, I also thought about what a numerical warning label is likely to do inside the human mind. We imagine it lowers the reader’s confidence. It does not. It sits above or below the number, and the number is what stays. Tell someone their life expectancy estimate is 79, wrap it in six paragraphs of statistical humility, and ask them to come back two weeks later. It’s unlikely that they will remember the humility. They will remember 79. A few will be frightened in a way that helps nobody, and those few will often be the people who answered the question about anxiety and depression honestly. I took the numbers out of the conclusion.

Not softened, not hedged, not padded the language with the words “might” and “suggests”. Removed them, with a written instruction that the tool must refuse to produce one even if the user asks directly, and must explain why.

Does The Dashboard Idea Even Work?

Having taken the roof apart, it seemed fair to look at the foundation. Starting with the car, since I opened the article with it. Sanguinetti and colleagues (2020) pooled 17 studies of in-car fuel economy feedback. The average improvement is 6.6%. That is real and worth having, yet a good deal smaller than the story I have been telling you.

Two details matter here more than the headline. The feedback that worked best combined the instant reading with the running total. And separately, the effect shrank the longer the system was in place, as drivers stopped noticing a screen that was always there.

Now a second dashboard, one you have probably driven past. Those roadside signs that flash your speed back at you as you approach. Flynn and colleagues (2020), pooling 43 studies, found they cut car speeds by about 4 miles per hour. That sounds trivial until you learn what 4 miles per hour buys at 30 to 35 miles per hour: up to 40% fewer deaths when a car strikes a person on foot. Look at the two together and a pattern appears. Both signals are immediate. Both refer to something your body is doing at that exact second. Both are attached to a small, specific action: lift your foot.

Where those conditions hold, feedback works, modestly, and fades as people get used to it. A predicted age of death has none of those properties. You read it once. It refers to something decades away. It is attached to no particular action at no particular moment. As such, my own analogy breaks at precisely the point where my argument needed it to hold.

Then I Checked The Premise

My whole idea rested on an assumption: that showing people their personal risk changes what they do. I had never examined it. The evidence is not kind. French and colleagues (2017) came at this from above. Rather than running another study, they gathered 9 separate reviews of the existing evidence, which between them covered 36 studies, some appearing in more than one review. Their conclusion was that presenting risk information on its own, even when it is highly personal, does not produce strong or lasting changes in behaviour. Not one of those 9 reviews reached a more hopeful verdict.

Hollands and colleagues (2016), writing in the BMJ, looked at perhaps the most personal risk information of all: your own DNA. They found that telling people about their genetic risk had little or no effect on smoking, diet or exercise. It did not even change what they intended to do. The kind of tool I was building has been examined too. Bonner and colleagues (2019) judged the NHS Heart Age Test against the standards used for screening programmes and found it failed nearly all of them. No trial shows it saved lives. Of roughly 2 million users, 78% were told their heart was older than their real age.

A tool that tells three quarters of a country it is ageing badly, with no proven path for what happens next, is not obviously a gift to anyone.

The Bigger Objection

There is an older and harder version of this argument, worth knowing even if you never touch my questionnaire. Rose (1978) published a paper called “Sick individuals and sick populations”. It is one of the most quoted papers in public health, and its argument is simple: there are two ways to prevent disease. You can find the individuals at high risk and work on them. Or you can change the conditions that produce the risk in everyone.

Rose showed that the first approach, the one that feels obvious, achieves less than people expect. Most cases of most diseases come not from the small group at high risk, but from the very large group at moderate risk, simply because that group is so much bigger. Sorting individuals finds markers of who is vulnerable. It does not touch the cause.

The History Supports Him

In 1854, during a cholera outbreak in London, John Snow traced the deaths to a single public water pump on Broad Street, and had the handle removed. Nobody was persuaded of anything. The water simply stopped being available. Even this story is tidier than the truth, since the outbreak was already fading when the handle came off. The principle holds: you do not teach people out of cholera; you take away the pump.

Closer to living memory, Britain spent years campaigning for people to wear seat belts. By the end of all that campaigning, roughly 40% of drivers and front seat passengers were wearing one. In January 1983 it became the law, and wearing rose to around 95% almost immediately. The Department of Transport’s own analysis of police casualty records found that deaths then fell by 25% among drivers and 29% among front seat passengers, with serious injuries down 21% and 30% respectively. Years of information got to a 40% plateau. One change in the rules got the rest.

A third example sits closer to where I live, and it makes the point in a different way. In Cambodia, drowning is the leading cause of death among children. Hile Teuk Kampuchea, an NGO whose name means Swim Cambodia, reports that around 2,000 children drown here every year, which is roughly 6 a day. The organisation could have run a campaign telling parents that water is dangerous. Parents in a country of rivers, ponds and flooded rice fields already know that water is dangerous. Instead it teaches children to swim, trains them in survival skills, and prepares teachers so that water safety sits inside the school day rather than on a poster.

Notice what that is. It is not aimed at the children most at risk, identified in advance by some questionnaire. It is aimed at all of them, and it moves the whole group a little further away from harm.

That is Rose’s population strategy in its plainest form, and it is the difference between telling people about a risk and changing what they are able to do about it. The most sobering evidence is recent, and it comes from Sir Michael Marmot. He chaired the World Health Organisation’s commission on the social determinants of health, and his 2010 review became the reference point for health inequality policy in England. Ten years later he went back to look at what had happened. Marmot and colleagues (2020) found that for the first time in more than 100 years, life expectancy in England had stopped rising. It stalled between 2010 and 2018. For women in the poorest tenth of the country, it did not merely stall. It fell. The report puts this down to child poverty, housing, the loss of local services, and deaths from suicide, drugs and alcohol among working age adults. However few in that account died prematurely of a failure to know of those risks.

Here I have to be careful, having spent this whole article objecting to overreach. A national trend says something about where the leverage sits. It says nothing about what a questionnaire does to the person filling it in. Mixing those two levels is a well-known way to reach a confident wrong answer, and I am not going to pretend Marmot’s figures are evidence about my tool. They are evidence about the size of the thing my questionnaire is not touching. What the record does support is a question about effort. If the large gains come from prices, laws, housing, clean air and clean water, then a personal risk score is not merely imprecise. It is aimed at the wrong level.

It asks an individual to solve, alone and after the fact, something that keeps being produced upstream.

What About Nudge Theory?

A fair objection at this point is that there is a middle ground between informing people and regulating them, and it has a name. Nudging changes the setting rather than the message: put the healthier option at eye level, make the pension the default so people have to actively choose whether to opt out, or reword that key letter so the form actually gets returned. It is one of the most influential ideas in behavioural policy of the last 20 years, and it is, in principle, exactly the sort of thing I have been arguing for.

The difficulty is not that nudging does not work. It does. The difficulty is that its effects are usually much smaller than the enthusiasm surrounding it suggests. Mertens and colleagues (2022) pooled the nudge literature and reported an effect that looked healthy, at 0.43 in the standard units’ researchers use. Maier and colleagues (2022) took the same data and corrected it for publication bias, which is the tendency for studies that find something to get published, while studies that find nothing sit in an unclaimed drawer. Corrected, the effect fell to 0.04, which is close enough to nothing that the authors said so in their title.

Then the real world. Della Vigna and Linos (2022) examined 126 trials run by two large government nudge units in the United States, covering more than 23 million people. Nudges in academic journals showed an average effect of 8.7 percentage points. The same kinds of nudges, run at scale by the people whose job it is, produced 1.4 percentage points. Real, worth having, and roughly six times smaller than the published literature suggests.

I take two things from this. The first is that nudging works, but modestly. That is not a criticism. A 1.4 percentage point improvement applied to 23 million people is a great deal of good, and it is still cheaper than almost anything else on the list. The mistake is expecting a nudge to transform behaviour on its own. The second is that we should be much more honest about what nudging can achieve.

An effect that is genuine, modest, and repeatable is useful. It only becomes disappointing when we compare it with a promise nobody could keep. Small and honest is not the same as useless.

What Is Left

Less than I hoped, and more than I expected. My original questionnaire no longer gives you a number. It gives you a sorted list of the things you could change, largest first, in your own words, and a short set of questions to take to your next GP appointment. That is a weaker instrument than a dashboard, but an honest one.

The part I now think matters most is the 20 minutes spent answering them properly. Sitting down and being asked, one question at a time, when you last had your blood pressure checked, and how your mother died, and whether you have someone to call at three in the morning, is the useful part. The report at the end is closer to a receipt.

What Is Coming, And What To Make Of It

Health dashboards are continuously evolving, and they will not look like mine. The use of the glucose monitor is the clearest example. It was built for people with diabetes, and it does what a good dashboard is supposed to do: it shows you, within minutes, what a particular meal did to you. Immediate, repeated, attached to an action you are taking now.

Access to affordable smart watches, that already estimate sleep stages and heart rhythm will help close the gap. As AI improves, more of this will be stitched together, and the sales pitch will be a single score that describe how you are doing.

Some of that is worth welcoming. A measurement close to the action beats a lecture about a risk you will face decades away, which is the whole argument of this article. Continuous data can catch things early that an annual appointment misses. For people far from a clinic, and for the many countries where seeing a doctor means a journey and a lost day’s pay, a decent, accessible and affordable smart tool in a pocket is not a gimmick.

There is, a place for dashboards. I have perhaps been too hard on the idea itself. The useful dashboard is not the one that simply tells you how healthy you are. It is the one that sits inside a lifestyle and a cycle of action. It shows you something you can change, gives you reason to change it, lets you see what happened when you did, and furthermore gives you a reason and incentives to do it again.

The dashboard is less a display than part of a feedback system: measure, act, see the result, adjust, repeat. The incentive matters too. It does not have to be financial. It might be reaching a milestone, unlocking the next stage, receiving positive reinforcement, meeting a challenge, or simply seeing that something you did produced a better result. The important thing is that the information has somewhere to go.

A dashboard that produces information and stops there is just another form of advice. A dashboard connected to achievable actions, meaningful incentives and repeated feedback can become part of the behaviour itself. This is not only intuition. It is what Sanguinetti and colleagues found in the driving data: the feedback that worked best paired the instant reading with the running total, and comparison standards, game elements and small rewards all pulled in the same direction.

Three Things Are Worth Doubting

The first is precision theatre, which is the failure I have just described in my own work. A number carried to one decimal place, produced by a system with no idea how wrong it might be, will always feel more authoritative than it deserves. Watch for tools that tell you what your reading is without telling you how uncertain it is.

The second is who gets them. If the people who benefit are those who already have money, time, a good phone and a doctor to interpret the output, then the technology widens exactly the gap Marmot spent his career describing. A tool that helps the comfortable and misses the poor makes the population figures worse while every person using it reports feeling better served. The country is told it is getting healthier. Only the better placed actually are.

The third is what happens to the data. A continuous record of your body is the most intimate thing you will ever generate, and it is being generated on someone else’s servers, under terms almost nobody reads, has been consulted on or agreed to. The question of who can see it, and what follows for insurance and employment purposes is not a footnote to the technology. It is the technology. None of that argues against building these things. It argues for building them honestly, and for asking harder questions of the people who design and sell them, including the ones who write articles about how thoughtfully they built theirs.

If You Want The Prompt

I have not pasted it at the bottom of this post, for a reason. Questions about your parents, your sleep and your fears are not something to hand out like a leaflet, and I would rather send it with a note about what it will and will not do. Message me and I will send it over. It is free, it works in any of the main AI assistants, and it takes about 20 minutes.

Three honest warnings before you ask for it. It is not a medical assessment, and I am not a doctor. The entire purpose of the output is to send you to one better prepared than you would have otherwise arrived. You use it at your own risk, and I accept no liability for anything you do, or do not do, as a result of it. Your answers never come to me. The conversation happens between you and whichever AI Assistant you use. I have no access to it, no copy of it, and no way of seeing what anyone types. Nothing is sent to me, collected by me, or stored by me at any point.

What I cannot promise is what your AI LLM Assistant does with it. You will be typing your family medical history into someone else’s chatbot. Whether that is kept, reviewed by a person, or used for training is decided by that company’s policy and your own settings. Check them first. Use a private or temporary chat if you have one. Skip anything you would rather not have written down.

I still believe the dashboard problem is real, and that making slow burning risks visible is worth working on. I no longer believe you get there by inventing a number precise enough to frighten someone. I am now fairly sure that even a true number would not do the work we keep hoping it will do.

What is left is smaller and more useful. Show a person the two or three things genuinely within their reach. Give them a meaningful way to act on those things, see what happens, and have a reason to keep going.

Be honest that the showing is the easy part, and that the doing belongs to them, their doctor, and the conditions they happen to live in. That is a modest offer. It is also, on the evidence, about as much as a set of questions can honestly promise.


References

Bonner C, McKinn S, McCaffery K, et al. Is the NHS ‘Heart Age Test’ too much medicine? British Journal of General Practice 2019;69(688):560-561.

DellaVigna S, Linos E. RCTs to Scale: Comprehensive Evidence from Two Nudge Units. Econometrica 2022;90(1):81-116.

Durbin J, Harvey A. The Effects of Seat Belt Legislation on Road Casualties in Great Britain. Department of Transport, HMSO, 1985. With Scott PP, Willis PA, Road Casualties in Great Britain: the First Year with Seat Belt Legislation, TRRL, 1985. Wearing rates and casualty reductions as summarised in the RoSPA Road Safety Observatory synthesis on seat belts.

Flynn DFB, Breck A, Gillham O, Atkins RG, Fisher DL. Dynamic Speed Feedback Signs Are Effective in Reducing Driver Speeds: A Meta-Analysis. Transportation Research Record 2020;2674(12):481-492.

French DP, Cameron E, Benton JS, Deaton C, Harvie M. Can Communicating Personalised Disease Risk Promote Healthy Behaviour Change? A Systematic Review of Systematic Reviews. Annals of Behavioural Medicine 2017;51(5):718-729.

Hile Teuk Kampuchea (Swim Cambodia). Drowning figures and programme description from the organisation’s own published material. These are the NGO’s figures rather than independently audited statistics.

Hollands GJ, French DP, Griffin SJ, et al. The impact of communicating genetic risks of disease on risk-reducing health behaviour: systematic review with meta-analysis. BMJ 2016;352: i1102.

Maier M, Bartoš F, Stanley TD, Shanks DR, Harris AJL, Wagenmakers E-J. No evidence for nudging after adjusting for publication bias. PNAS 2022;119(31): e2200300119.

Marmot M, Allen J, Boyce T, Goldblatt P, Morrison J. Health Equity in England: The Marmot Review 10 Years On. Institute of Health Equity, 2020.

Mertens S, Herberz M, Hahnel UJJ, Brosch T. The effectiveness of nudging: a meta-analysis of choice architecture interventions across behavioural domains. PNAS 2022;119(1): e2107346118.

Rose G. Sick individuals and sick populations. British Heart Journal 1978; 40:1069-1077. Reprinted in International Journal of Epidemiology 2001;30(3):427-432.

Sanguinetti A, Queen E, Yee C, Akanesuvan K. Average impact and important features of onboard eco-driving feedback: a meta-analysis. Transportation Research Part F 2020; 70:1-14.


Interview: Veena S Rao, ACPN Director, India

IN A NUTSHELL
Editor's note
A highly accomplished professional with extensive experience in addressing undernutrition and micronutrient deficiency in India, Ms. Veena S Rao has served in the Indian Administrative Service (IAS) from Karnataka Cadre, and retired in 2009 as Secretary to the Govt of India, Ministry for the Development of the North East Region.

She has worked both in the Govt of Karnataka and Govt of India, and also has international experience, particularly with UN Agencies, World Bank and Asian Development Bank.

After retirement She was Advisor, Karnataka Comprehensive Nutrition Mission, an initiative spearheaded by her with the Government of Karnataka to address undernutrition and micro nutrient deficiency in Karnataka, following the inter-generational, inter-sectoral strategy, and addressing the direct causes of undernutrition and micronutrient deficiency in India, namely, information deficit and need for behaviour change, dietary deficit, inter-sectoral convergence through simultaneous operation of ongoing nutrition/health related interventions, particularly relating to immunization, safe drinking water and sanitation, and vigorous, real time monitoring; and the market deficit.
She is presently Director, Auro Centre for Public Nutrition, Public Health and Public Policy, Bangalore, a vertical set up by her in Sri Aurobindo Society, Puducherry.

In this connection, PEAH had the pleasure to interview Ms. Veena S Rao relevant to her recently released book India’s Undernutrition and Human Capital: Addressing the Roots

By Daniele Dionisio

PEAH – Policies for Equitable Access to Health

  INTERVIEW

Veena S Rao

Auro Centre for Public Nutrition, Public Health and Public Policy (ACPN)

Bangalore, India

By Ms. Veena S Rao already published on PEAH: see HERE

–PEAH: Nice to meet you Ms. Rao. Your professional career makes you an acknowledged expert on conceptualizing Policy and Programming for Health and Nutrition, whereby Programme Implementation, Programme Management and Monitoring, and IEC (Information, Education, and Communication) and Behaviour Change for Health and Nutrition play a fundamental role. What’s your say while linking these to the foundation of your book? 

–Rao: Thank you for your very complimentary words.  I have always held that the root causes of chronic poor health/nutritional status of a large section of our people are extremely complex and inter-sectoral – ranging from dietary deficit which is accepted as a given in poor households; information deficit regarding balanced diets within family budgets which has led to unhealthy dietary behaviours hardened over generations; superstition regarding complementary feeding for infants and weight gain during pregnancy; lack of knowledge regarding the importance of safe drinking water and proper sanitation and how they protect against infection and improve the health and nutritional status of all age groups in the family, and very importantly, female literacy.  I think I have made all these linkages in my book.

–PEAH: World Bank Blogs on February 18, 2020 featured a successful pilot project led by you and  completed with exceptionally positive results and improvement in the health and nutritional status of the target groups. Can you let us in on it, just to add context to the book’s contents? 

–Rao: Well, in a nutshell I can say that I put into practise whatever I preached! With support from the Karnataka State Government and the World Bank, we finalized an Intersectoral/Intergenerational  Strategy which we implemented in all villages in two of the poorest Blocks (Development Units of a District) of Karnataka, Chincholli Block, Kalaburgi District (136 villages)and Devadurga Block in Raichur District (173 villages)  targeting the two poorest quintiles of the Blocks covering around 12,560 infants below 3 years, 16,503 adolescent girls 11-18 years,  1624 pregnant women and 3750 lactating mothers when we strated. This was an open expirement wherein beneficiaries within the target groups could leave and return, and new beneficiaries could join. Interventions can be sumarized as 1) Addressing the Information Deficit within the family and community through a continuous but phased multimedia Awareness Generation/Behavior Change Campaign covering basic aspects of child, adolescent and maternal care; dietary diversification within family budgets, in keeping with locally available agricultural and horticultural produce and cultural practices; hygiene and sanitation. 2) Bridging the Dietary Deficit by providing appropriate fortified supplementary nutrition to the 3 target groups which was produced by local Women Self Help Groups; creating demand among communities for ongoing government programmes, particularly health and sanitation programmes, and lastly Real Time Monitoring which gave us real time information of health/nutritional improvements of target groups within families or of any bottlenecks or course correction which were needed. The pilot projects addressed the root causes and brought about very quick improvement in the health and nutritional status of the target groups, reduced incidence of low birth weight babies. Details have been provided in Chapter 7 of the book, “A Strategy that Worked: Karnataka Comprehensive Nutrition Mission.”

–PEAH: You currently serve as Director, Auro Centre for Public Nutrition, Public Health and Public Policy. Relevantly, what as regards your aims and inside strategy in unison with the book scope? 

–Rao: The objectives of Auro Centre for Public Nutrition, Public Health and Public Policy (ACPN) are to strengthen our human capital and demographic dividend through impactful inter-sectoral strategies, interventions and convergence at grassroots; to promote research and develop activities for providing information and knowledge to students, professionals, community organizations, panchayats (village elected bodies) and women self-help groups regarding a) The continuum of nutrition, health, education, skills, across the life cycle and b) The inter-sectoral, inter-generational aspects of human development, covering public nutrition, public health, education, skills, learning and livelihoods, and their impact on human capital, reduction of poverty and on economic progress of individuals, communities and the country.

Indeed, the contents of the book cover all these aspects in a wide but simple structure tailored to addressing the grassroots, where the action must really happen.

–PEAH: As in the official brochure, your book explores the undernutrition situation in India and its repercussions on the country’s human capital, from a public policy practitioner’s approach. It critically examines government policy since independence to the present time and foregrounds the issues that have led to the persistence of poor nutritional and health status among a large section of India’s population. In this vein, chapters span across and cover critical issues including, among others, the deep rootes of India’s undernutrition and dietary deficiences and how do improve India’s nutritional and health status within a generation.  Can you tell us more as regards the last theme? 

–Rao: To begin with, the linkages between health and nutrition to strong human capital and economic growth should seriously enter the public policy domain, so that there is high level public discussion on the subject. Yes, India’s nutritional and public health indicators can be improved faster within a generation if the root causes, what I call the Triple Deficit, are addressed – the Dietary Deficit, the Information Deficit and the Market Deficit. And structurally, these can be best addressed by a minimal inter-sectoral and intergenerational convergence of ongoing government programmes relating to health, nutrition, childcare, education, water and sanitation programmes at family level, and a working system of real time monitoring to ensure that these programmes are reaching every targeted family. Government must focus on the most vulnerable families, provide an additional hand at the village level for this work, leverage the corporate sector and all national and international stakeholders to achieve results.

–PEAH: The volume traces the complex history of public nutrition and public policy in India, and presents a sound multi-sectoral, intergenerational strategy which has been successfully piloted, and can be scaled up across chronic undernutrition pockets of India. Can you elaborate on these points? 

–Rao: The multi-sectoral, intergenerational strategy aimed to address the root causes by:

– Adopting the intergenerational, life cycle approach by addressing the nutritional needs of infants, children, adolescent girls and pregnant and nursing mothers.

– Bridging the calorie–protein–micronutrient deficit among the intergenerational target groups by providing appropriate energy-dense fortified supplementation for consumption.

– Accelerating, integrating and tightly monitoring multi-sectoral ongoing programmes that have an impact on malnutrition, such as Immunization and Vitamin A Supplementation, Anaemia control, Water and Sanitation, etc., and achieving convergence between the ongoing programmes so that they operate simultaneously and filling programmatic gaps.

– Increasing programme coverage by demand creation by involvement of the community, NGOs, SHGs and VPs.

– Launching a sustained general public awareness campaign, through the multimedia and interpersonal communication mode to reach the general public, especially at the grassroots, regarding proper nutritional practices within existing family budgets and proper child and maternal care and create demand for government programmes.

– Making available low-cost energy foods for the general population through Public-Private Partnerships.

This strategy has proved successfull and has been validated in the Karnataka Multisectoral Nutrition Pilot Projects, and can be scaled up to cover chronic undernutrition pockets of India

–PEAH: Who is the book for? 

–Rao: This book is definitely meant for students of Public Health and Nutritional Sciences, Professionals in any sector of Development, both governmental and non-government, NGOs and Field Workers.

I also believe that policy makers should take a good look at this book, particularly since we are depending so heavily on our human capital and demographic dividend – the largest workforce in the world aged 15-59 years – for our future economic growth and becoming a developed nation. And I also see that increasingly, the whole question of Human Development is taking a bit of a back seat in national debate – much greater emphasis is on AI and other frontier technologies, which are no doubt very important, but I do believe that human development should receive equal priority from government if we want to become a developed country.

The last para of my book says it all

“A global power with developed infrastructure and underdeveloped human capital would suffer from acute social contradictions and bipolarity, both nationally and internationally. Strengthening our human capital across all age groups, which constitute our present, immediate and future demographic dividend, and enabling it to achieve its complete physical and cognitive potential, can only result in better health, learning ability and education among children and adolescents, in acquiring higher skills and increased capacity for physical work, and securing better employment, greater upward mobility and higher incomes. This immediately translates to lower unemployment rates and higher GDP for the country, but a GDP based on greater financial and intelligence quotient (IQ) inclusion, and lower dependence on government for healthcare, food security and nutrition, education and employment. The government must overcome its own policy and programme deficit, show its seriousness and start addressing this issue urgently through new ideas and innovation on the ground, as we approach our US$5 trillion economy and the advent of artificial intelligence.” 

–PEAH: Aiming to fill the nutritional gaps you are dealing with, which partners do you currently count on? 

–Rao: A very difficult question. Presently, I can only count on government. It appears to me that most non-government and corporate agencies are bound by the mandates of their funding agencies which focus on certain isolated aspects of undernutrition and poor health – for example, school mid day meals programmes, fortification, anaemia, or support ongoing government programmes in Districts. In the recent past, I am not aware of any agency funding a programme which covers and addresses minimal intersectoral aspects of poor health and undernutrition simultaneously, which alone can create impact. So, perhaps, we need to convince them and change their mind set as well.

–PEAH: Thank you Ms. Rao for the excellent work linking advocacy to scientific and humanitarian commitment.

–Rao: Thank you. My pleasure.


News Flash 678: Weekly Snapshot of Public Health Challenges

News Flash Links, as part of the research project PEAH (Policies for Equitable Access to Health), aim to focus on the latest challenges by trade and governments rules to equitable access to health in resource-limited settings

Needlefish (Belone belone)

News Flash 678

Weekly Snapshot of Public Health Challenges


How Much is the EU’s Proposed Development Budget for 2028-2034 Really Increasing?

Public finance conference 2026: health spending under pressure Date 29 Sep – 30 Sep 2026

UN Tax Convention negotiations: State of Play and joint civil society inputs

Webinar registration: The EU & Allies’ Positions in the PABS Negotiations Under Human Rights Scrutiny Sep 10, 2026

Behind the scenes of the pandemic agreement

Medico International: 10/22/2026 – 10/23/2026 | Frankfurt Public Pharma for Europe: 2nd Public Pharma Conference

Antimicrobial stewardship in low- and middle-income countries: Access versus adherence

Webinar registration: Understanding Trust in Integrated Care Through the Lived Experiences of MND Sep 23, 2026

WHO validates Bhutan for eliminating dog-transmitted human rabies

WHO validates Timor-Leste’s elimination of trachoma as a public health problem

Global and regional progress towards reduced burden of oral conditions between 2019 and 2023: a systematic analysis for the Global Burden of Disease Study 2023

The long wait for fistula surgery in Liberia

Ebola response in eastern DR Congo must include food assistance, WFP says

HRR833. FORMAL EQUALITY EXISTS ON PAPER; INEQUALITY EXISTS IN PEOPLE’S LIVES. (Esteban Gonzalez P.)

To bridge the evidence gap in women’s health, look at the real world

AI could pose ‘existential’ risk to humanity, UN rights chief warns

Immigration in Sweden: how the country went from one of Europe’s most welcoming, to one of its most restrictive

UN Votes to Adopt New World Map That Shows Africa’s True Size

Health Advisory Council: Urgent health update: Consequences of war on Gaza, the West Bank/East Jerusalem, and Lebanon – September 5, 2026

Cuba Under Economic Siege: Evidence of the Humanitarian and Health Consequences of United States Coercive Measures and Arguments for an Equity-Based Response  by Juan Garay

Sudan’s healthcare system on brink of collapse after cuts, medical charity warns

Namibia: Drought displaced Angolans face human rights abuses

Special edition: Africa’s massive food systems conference zeroes in on youth

Indonesian Wildfires Cause Air Pollution Levels to Rise to Hazardous Levels in Southeast Asia

Wildfires, heat waves threaten to undermine air quality, UN weather agency says

Global health’s great derangement

Nepal puts climate justice at centre of global pitch for flood aid

Nepal flood disaster exposes cascading threats in Himalayas

You Don’t Know How Connected You Are to Nature

The Global Framework on Chemicals – First International Conference (IC1) 16-20 November 2026, Geneva, Switzerland


Cuba Under Economic Siege: Evidence of the Humanitarian and Health Consequences of United States Coercive Measures and Arguments for an Equity-Based Response

IN A NUTSHELL
Author's note
Can the progressive deprivation of essential conditions for life constitute a “genocide without weapons”? An analysis from the perspective of public health and Sustainable Health Equity

By Juan Garay[1]

SHEM[2] Co-Chair and Professor of Health Equity (Cuba, Mexico, Brazil, Spain)

By the same Author on PEAH: see HERE

Cuba Under Economic Siege

Evidence of the Humanitarian and Health Consequences of United States Coercive Measures and Arguments for an Equity-Based Response


I. Introduction

The purpose of this study is to contribute to a better understanding of recent trends and the current situation in Cuba in the social, political, economic, and health sectors, as well as to identify possible priorities for collaboration and cooperation.

This is the third article by the same author in the last three months addressing the health situation and challenges in Cuba. The previous articles analysed the humanitarian health crisis[3] and the risks of increasing inequity associated with neoliberal reforms of the private economy and their relationship with the selective United States economic siege.

The current analysis must be placed within a particularly complex context. The United States economic, commercial, and financial embargo and sanctions, intensified during 2026 and with increasing effects on third parties and, particularly, on access to fuel, are combined with internal factors that limit the country’s productive, financial, and administrative capacity. Declining domestic production, difficulties in importing essential goods, the energy crisis, the loss of capacity in public services, migration, and rapid population ageing are increasingly affecting living conditions and the capacity of the State to maintain basic services.

The latest available official data, corresponding to 2024, show a significant deterioration in some mortality indicators. The analysis conducted in this study estimates, in comparison with different historical and demographic references, an annual excess mortality of around 14,000 deaths and a loss of more than 100,000 years of life due to premature deaths associated with recent changes in mortality rates. These estimates should be interpreted as analytical calculations rather than official records of avoidable mortality.

Socioeconomic and migration trends, together with the deterioration of certain capacities within the social and health systems, suggest a possible worsening of this trend during 2025 and 2026. The available information on infant mortality, although still incomplete and showing important differences between territories, represents a warning signal. The national infant mortality rate may have increased to approximately 9.9 per 1,000 live births in 2025, compared with an average of around 4.4 per 1,000 during the previous fifteen years. Particularly high increases have also been observed in some municipalities analysed during the mission. These local data require confirmation through consolidated national statistics, but they justify priority monitoring.

The Cuban health system retains important structural strengths: universal coverage, an extensive primary health care network, historically high availability of health professionals, domestic training of human resources, and long experience in public health, prevention, and vaccination. However, these capacities are under increasing pressure. The reduction in the number of professionals, difficulties in importing raw materials, medicines, equipment and spare parts, problems in production and distribution, the energy crisis, and transport difficulties are progressively affecting the effective capacity of the system to provide timely and equitable care.

Access to medicines is one of the main critical areas. The irregular availability of essential medicines has contributed to the expansion of an informal market in which the prices of some treatments represent a very high proportion of the income of public-sector workers and pensioners. This situation may transform chronic diseases that are normally manageable into additional sources of inequity and mortality, particularly among older people and households without stable access to foreign currency or remittances.

The analysis of the burden of health inequity developed in this study, using historical, territorial, and international references, makes it possible to estimate part of the mortality and potential years of life that could be avoided through improvements in social, economic, environmental, and health conditions. The results suggest that recent deterioration affects not only national averages but may also be widening differences between age groups, sexes, and territories.

At the same time, growing economic inequality can be observed between people with access to income in foreign currencies, remittances, or private economic activities and those who depend mainly on public salaries or pensions. The development of micro, small, and medium-sized enterprises has created new opportunities for employment and income, but it has not compensated for the loss of capacity of the public sector to guarantee universal services. In addition, an important proportion of private activity is concentrated in trade and the importation of consumer goods, while national productive capacity for essential goods remains limited.

In this context, it is particularly important to protect effective and equitable access to essential medicines, primary health care, adequate food, water, energy, transport, and other fundamental determinants of health. International cooperation can play an important role if it is directed towards preserving public capacities, strengthening national production and distribution, and reducing inequalities in access.

Based on the analysis conducted, possible priority areas for collaboration include support for primary health care professionals and services, strengthening equitable access to essential medicines, improving storage and distribution systems, supporting academic and health institutions, restoring national pharmaceutical production capacities, and promoting sustainable solutions in energy, water, and food.

II. Health in Cuba before 2020

The demographic, political, economic, and psychosocial complexity of Cuba, together with existing limitations in certain areas of economic and social information, makes it difficult to produce a precise picture of the current situation and, particularly, to develop short- and medium-term scenarios. For this reason, the present analysis combines official Cuban statistics, international sources, and estimates specifically developed for this study.

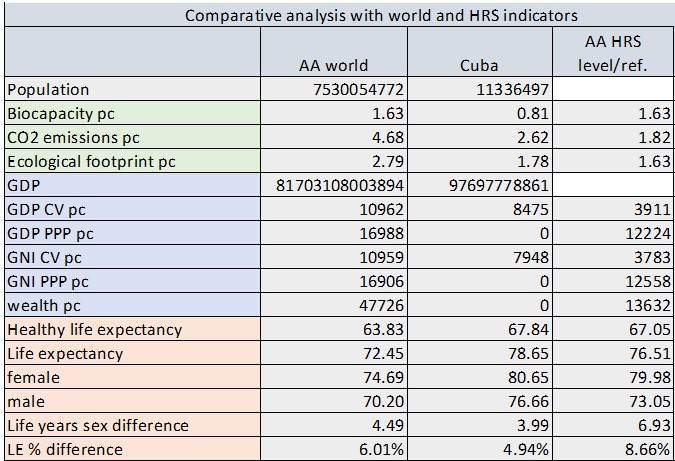
Until approximately 2015, Cuba showed an unusual combination of relatively high health and wellbeing indicators with levels of ecological resource consumption lower than those of high-income countries. According to the Sustainable Health Equity Atlas developed by J. Garay and the Sustainable Health Equity Movement (SHEM), Cuba was above the global average for certain health and wellbeing indicators while maintaining a relatively low ecological footprint.
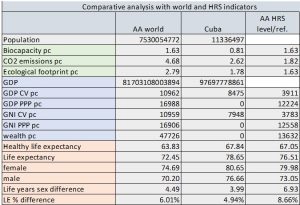
Table 1. Comparative analysis of economic, ecological, and health indicators for Cuba, the global average, and the Sustainable Equity reference

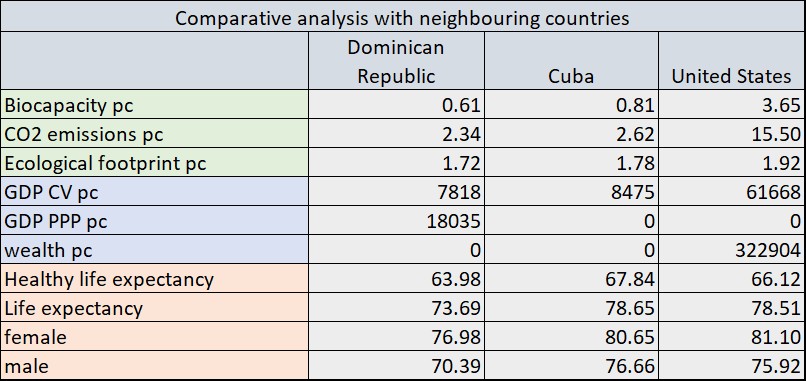
The comparison with the Dominican Republic is particularly illustrative. Both countries share certain historical, geographical, and demographic characteristics, although they have followed different economic and political trajectories. Until approximately 2020, Cuba had a life expectancy nearly five years higher than that of the Dominican Republic, with a difference of more than six years among men. This health advantage was achieved with significantly lower levels of economic resources and ecological consumption than those of high-income countries.
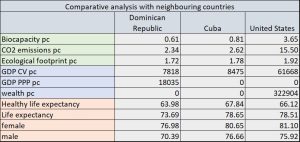
Table 2. Comparative analysis of economic, ecological, and health indicators for Cuba, the United States, and the Dominican Republic

Source: Sustainable Health Equity Atlas, J. Garay, SHEM[4]

The comparison with the United States is also significant. Despite the United States having a per capita biocapacity several times higher and a GDP per capita far above that of Cuba, Cuba’s life expectancy until approximately 2020 was comparable and, in some groups, slightly higher, particularly among men. This difference is one of the factors supporting an analysis of the Cuban experience from the perspective of social efficiency and equity, without ignoring its important economic and political limitations.

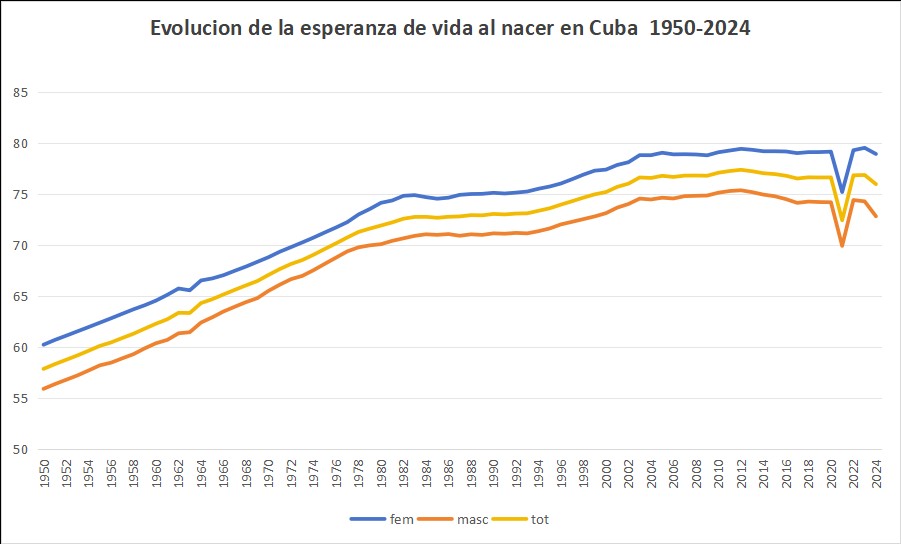
Since 2020, however, health indicators have shown significant deterioration. The pandemic caused a substantial increase in mortality and a decline in life expectancy to levels not observed for previous decades. In 2021, life expectancy fell to approximately 73.2 years. This was followed by a partial recovery during 2022 and 2023, but data for 2024 show a further deterioration.

Analysis of data from the Statistical Yearbook of Health indicates that in 2024 life expectancy declined by approximately 1.1 years compared with 2023, according to the calculation used in this study, accompanied by an increase in mortality adjusted for demographic structure. Estimated excess mortality compared with 2023 was around 13,800 deaths.

The absence of consolidated statistics for 2025 and 2026 requires subsequent trends to be interpreted with caution. Nevertheless, the increase in infant mortality reported in 2025 and data obtained in some municipalities during 2026 are warning signals that support the hypothesis of a possible worsening of health conditions. This hypothesis should be tested when complete national statistics become available.

III. Demography

Demographic change is one of the main structural factors shaping the current situation. Cuba increased from approximately seven million inhabitants in 1959 to nearly ten million by the mid-1980s. Since then, population growth has stopped and, since approximately 2019, the population has entered a period of decline.

Current estimates place the resident population at around 9.5 million people, although the effective figure may be lower if people who have recently emigrated but remain administratively registered as residents are taken into account.

Historically, Cuban migration has been directed mainly towards the United States, followed by Spain and Mexico. In recent years, new migration routes towards Latin America, including Brazil, have developed. For part of the low-income population, migration involves the sale of family assets, particularly homes, in order to finance documentation, transport, visas, and initial settlement costs.

Migration has also begun to modify the sex structure of the population. Until approximately 2012, more men than women lived in Cuba, whereas this relationship subsequently reversed and there is now a slight female majority. This phenomenon may be related both to migration, which affects particular age and sex groups differently, and to the greater proportion of women at older ages.

Population ageing is another major challenge. Approximately one quarter of the population is currently aged 60 years or over. The birth rate has declined steadily over previous decades, and fertility is clearly below replacement level, at around 1.3 children per woman.

The combination of low fertility, migration, and increased survival during previous decades is producing rapid population ageing and a decline in the working-age population. This increases the dependency ratio and places additional pressure on pension systems, health care, and long-term care.

IV. Political context

Cuba maintains a political structure centred around the Communist Party of Cuba (PCC), constitutionally recognised as the leading force of society and the State. The PCC provides political direction to the main structures of government, including the Council of State, the Council of Ministers, and the country’s institutional system.

The National Assembly of People’s Power is the main representative and legislative body. Its members are elected through the constitutionally established electoral system, although the composition of national institutions remains closely linked to the political and social structures of the Cuban system. In addition to the PCC, social and mass organisations participate in institutional representation, including organisations representing women, students, farmers, and other social groups.

The process for approving major socioeconomic transformations reflects this hierarchical structure of decision-making. Strategic measures are discussed and approved within political structures before being submitted to the corresponding legislative bodies.

The main traditional media—television, radio, and the press—remain under State control. At the same time, social networks and digital platforms have become an increasingly important source of alternative information, debate, and circulation of opinions, although they are also exposed to misinformation and political polarisation.

In foreign policy, relations with the United States remain particularly tense, although some spaces for dialogue exist. Cuba continues to participate actively in the G77 and maintains political and economic relations with Venezuela, Russia, China, Vietnam, Mexico, Brazil, and other countries. The international situation and the tightening of United States sanctions have progressively altered opportunities for cooperation and trade.

V. The embargo, sanctions, and the international context

Specific consideration should be given to the evolution of the United States economic, commercial, and financial embargo. For decades, a system of bilateral restrictions has been maintained, accompanied by measures with extraterritorial effects, particularly following the Helms-Burton legislation.

During 2026, according to the information analysed during the mission, these restrictions have acquired new dimensions, particularly regarding access to fuel and the behaviour of third-party economic and financial operators. Secondary sanctions and concerns about regulatory risks may generate effects extending beyond the companies formally subject to sanctions.

This phenomenon is particularly relevant for humanitarian cooperation. International organisations, United Nations agencies, and NGOs may face difficulties in transporting or financing certain donations when shipping companies, banks, or suppliers adopt policies of sanctions over-compliance.

The practical consequence is that medicines, food, agricultural equipment, and other goods intended for social programmes may be delayed or temporarily immobilised. These difficulties should be considered in any cooperation strategy intended to operate in Cuba, as they may affect both the cost and logistical feasibility of interventions.

At the same time, greater openness can be observed towards certain commercial flows linked to the Cuban private sector. This process may contribute to economic diversification, but it may also generate new inequalities if access to foreign currency, fuel, and imported goods becomes concentrated among groups with greater economic capacity.

From a public health perspective, the central question should not be limited to determining which actor is responsible for each restriction, but rather to analysing their concrete consequences for the availability of medicines, food, energy, water, transport, and health services, and to establishing cooperation mechanisms that reduce their effects on the most vulnerable populations.

VI. Economy

Limitations of information

The Cuban macroeconomic situation is particularly difficult to quantify. Official statistics do not always allow the full range of transactions carried out in foreign currencies or in informal markets to be reconstructed. This is compounded by multiple exchange rates, restrictions on banking liquidity, and difficulties in recording economic activities carried out outside official channels.

GDP per capita estimates produced by international organisations may be useful for international comparisons, but they do not necessarily reflect the effective purchasing power of the population. The existence of different exchange rates and the significant depreciation of the Cuban peso in informal markets mean that direct conversion of GDP and official salaries can produce very different results depending on the exchange rate used.

A significant proportion of economic transactions currently takes place through informal or semi-formal mechanisms. This particularly affects trade in consumer goods, medicines, foreign currencies, and certain services.

State sector

The State sector continues to play a fundamental role in the provision of social services, particularly health, education, social security, water, sanitation, justice, and other public services.

However, the loss of productive capacity, financial restrictions, infrastructure deterioration, and fuel shortages are reducing the effective capacity of these structures. In some services, informal payments or alternative mechanisms may emerge to compensate for the loss of workers’ purchasing power, with potentially negative consequences for access and equity.

The creation and expansion of micro, small, and medium-sized enterprises has introduced an important transformation. The establishment of an MSME can now take place relatively quickly, and thousands of formally registered private entities already exist.

The private sector offers salaries substantially higher than those available in the public sector and is becoming an increasingly important source of income for part of the population. However, a significant proportion of these activities is concentrated in trade, imports, and services, with still limited capacity to replace the State in the universal provision of social services.

Income and inequality

Public salaries and pensions have lost a substantial part of their purchasing power due to inflation and the depreciation of the Cuban peso. The figures used in this study place the average salary of workers in the budget-funded sector at around 7,000 CUP per month, while the incomes of many private-sector workers are several times higher.

Remittances from abroad are another fundamental component of household economies. Some studies have estimated flows close to US$2 billion annually. However, their distribution is highly unequal and depends mainly on the existence of relatives living abroad.

As a consequence, an economically differentiated society is emerging between those with access to foreign currency, remittances, or private economic activities and those who depend mainly on public salaries or pensions.

This transformation has important health consequences. When public services lose their capacity to provide services free of charge or at subsidised prices, the loss of purchasing power particularly affects households without access to foreign currency, increasing differences in nutrition, medicines, transport, and other determinants of health.

Informal economy

A growing proportion of economic activity takes place through social networks, digital platforms, and informal markets. These mechanisms make it possible to meet needs that cannot be adequately covered through official channels, but they often lack economic, fiscal, health, or consumer protection regulations.

The informal market for medicines is a particularly relevant example from a public health perspective. The availability of certain drugs may depend on travellers, intermediaries, and private networks, often at high prices and without sufficient guarantees regarding storage, authenticity, or quality.

Public assets

The State retains a very substantial proportion of the country’s land and productive and residential assets, as well as almost all State-owned hotel infrastructure. These assets represent considerable potential economic capacity, although their real value and capacity to generate liquid resources are difficult to estimate.

Any strategy for the use of these assets should be assessed not only from a financial perspective but also in terms of its distributive, environmental, and social consequences.

VIII. Ecology and sustainability

Cuba has high biodiversity and a natural heritage of considerable importance. Since the beginning of comparable international series, the country has maintained a relatively low ecological footprint per capita compared with high-income countries.

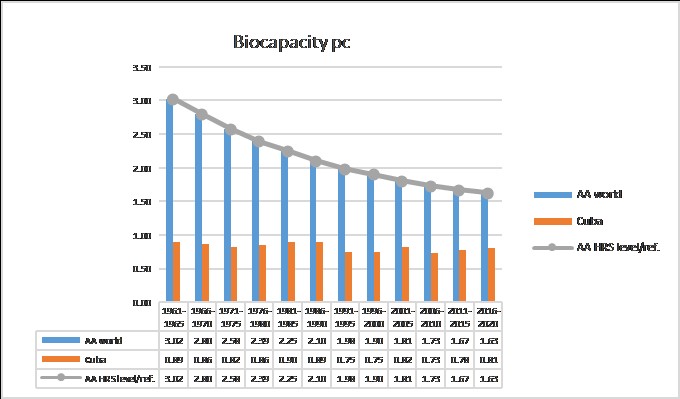
Cuban biocapacity per capita is approximately 50% below the global average. For long periods, the ecological footprint per capita has remained relatively close to the available biocapacity.
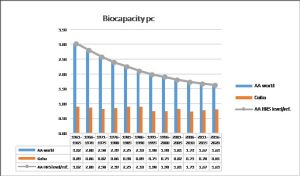
Figure 1. Evolution of per capita biocapacity in Cuba compared with the global average, 1960–2020

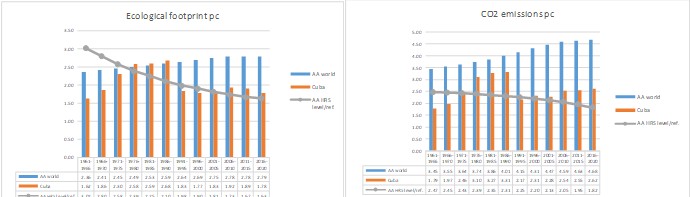
The carbon footprint has followed a different trajectory. Per capita emissions increased during certain decades, subsequently declined, and later returned to levels above those considered compatible with certain sustainability criteria.

The estimates used in this study place average emissions during 2015–2020 at approximately 2.5 tonnes of CO₂ per inhabitant, above a sustainability threshold estimated at around 1.8 tonnes.

Figures 2 and 3. Evolution of the ecological footprint and carbon footprint per capita in Cuba, 1960–2020, with reference to the ethical threshold of the planetary boundary

These emissions are nevertheless considerably lower than those of the United States and the European Union. The main issue for Cuba is not simply to reduce emissions, but to avoid a future economic recovery based on a model of consumption intensive in fossil fuels and imported goods.

The energy crisis has temporarily reduced some emissions, but the increasing dependence on imported goods may shift an important part of the environmental footprint abroad. The increase in waste from packaging and processed products is also becoming a growing problem in a context of weakening public collection and recycling systems.

IX. Society and living conditions

The energy crisis is currently one of the main determinants of living conditions. Insufficient fuel for thermoelectric power plants, together with breakdowns and deteriorating infrastructure, has produced significant deficits in electricity generation.

Irregular electricity supply directly affects other essential services. Water pumps depend on electricity, meaning that power cuts may result in interruptions to water supply. Internet access and communications are also affected.

Prolonged periods without electricity, water, or communication have cumulative effects on health. They make personal and household hygiene more difficult and affect food preservation, meal preparation, hydration, night-time rest, and the use of fans or other cooling systems during periods of extreme heat.

These problems disproportionately affect older people, households with chronic illnesses, persons with disabilities, and those without the resources to acquire generators, fuel, or private supply systems.

Cost of food and basic goods

Current prices of basic food products represent a very high proportion of public-sector salaries. The family food basket calculated for this study amounts to approximately 85,000 CUP per month.

Basic good / kg-l Price CUP Proportion of two average salaries Equivalent in Spain (€)
FOOD
Sweet potato 200 2.9% 60
Cassava 160 2.3% 48
Taro 400 5.7% 120
Rice 700 10.0% 210
Beans 800 11.4% 240
Lentils 1,000 14.3% 300
Eggs, one dozen 2,010 28.7% 603
Cooking oil 4,000 57.1% 1,200
Chicken (imported from the United States) 1,500 21.4% 450
Minced meat (imported from Brazil) 1,120 16.0% 336
Powdered milk 4,000 57.1% 1,200
Flour 1,000 14.3% 300
Salt 800 11.4% 240
Sugar 1,100 15.7% 330
Coffee 7,000 100.0% 2,100
Seasonal fruit 200 2.9% 60
Onion 1,200 17.1% 360
Garlic, one unit 40 0.6% 12
Bread roll 250 3.6% 75
White Cuban cheese 2,000 28.6% 600
Monthly family basket 85,130 608.1% 12,769.5
HYGIENE
Bar soap 350 5.0% 105
Detergent, 1 kg 1,500 21.4% 450
Toilet paper, one roll 200 2.9% 60
TRANSPORT
Journey of 2–3 km by tricycle 200 2.9% 60
Journey of 2–3 km by car 1,000 14.3% 300
OTHER EXPENSES
Restaurant meal 3,000 42.9% 900
One night in a hotel 21,000 300.0% 6,300
Bicycle 140,000 2,000.0% 42,000
Mobile telephone 91,000 1,300.0% 27,300
Rice cooker 95,000 1,357.1% 28,500
Washing machine 110,000 1,571.4% 33,000
Computer 350,000 5,000.0% 105,000
Electric tricycle 3,500,000 50,000.0% 1,050,000
Car 28,000,000 400,000.0% 8,400,000

Table 3. Prices of basic products in relation to the average State salary and equivalent costs in Spain

When this amount is compared with the average public-sector salary used as a reference, basic food for a family of four requires several monthly salaries. Housing, electricity, water, gas, transport, medicines, hygiene, and other essential goods must be added to these expenses.

The calculation used in this study places the minimum cost of a dignified life at around 210,000 CUP per month, although this figure should be considered an analytical estimate rather than an official poverty threshold.

The discrepancy between the official exchange rate and the effective exchange rate is one of the main factors required to understand this situation. Converting official salaries using the State exchange rate may provide a very different picture from the population’s actual purchasing power.

X. Psychosocial conditions

The material conditions described above also have psychosocial consequences. Economic insecurity, the migration of family members, separation from support networks, difficulties in accessing essential goods, and prolonged interruptions in electricity and water supplies may increase stress and social isolation.

Official information available on mental health is limited. Among the available indicators is the suicide rate, estimated at approximately 13.8 per 100,000 inhabitants, with a marked difference between men and women.

Dementia is also becoming an increasing cause of mortality in the context of rapid population ageing. The growing number of older people living alone or with reduced family networks creates an increasing need for community support services, care, and mental health services.

XI. Health

Life expectancy

Life expectancy is one of the most sensitive indicators for assessing overall changes in living and health conditions.

In 1959, Cuban life expectancy was around 63 years. It subsequently increased steadily, reaching approximately 77.4 years at the beginning of the 2000s.

After a period of stagnation, the pandemic caused an exceptional decline. In 2021, life expectancy fell to approximately 73.2 years. The subsequent recovery was partial, and the 2024 data again show deterioration.
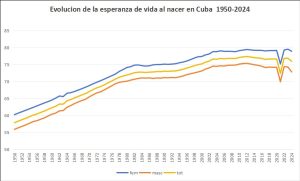
Figure 4. Evolution of average life expectancy at birth and life expectancy disaggregated by sex in Cuba, 1950–2024

According to the analysis conducted using available statistics, life expectancy in 2024 was around 75.4 years, with differences between men and women. These figures indicate a recovery from the 2021 low but do not yet demonstrate a sustained recovery to pre-pandemic levels.

Territorial differences are relatively moderate compared with those in other countries, although relevant variations exist. Guantánamo has one of the highest values, while the Isle of Youth has one of the lowest.

XII. Burden of health inequity

The calculation of mortality rates by age and sex and their comparison with different references makes it possible to estimate the potential burden of mortality associated with avoidable inequalities.

When Cuba in 2024 is compared with the average of the two decades preceding the pandemic, estimated excess mortality is approximately 11,349 deaths, of which around 65% occurred among men.

Compared with mortality rates in 2023, estimated excess mortality reaches approximately 13,783 deaths, with around 62% occurring among men.

Comparison with Guantánamo, used as an internal territorial reference, produces a higher estimate, close to 21,033 deaths. Comparison with an international Sustainable Health Equity reference, represented in this analysis by Sri Lanka, produces a different estimate of approximately 6,600 deaths.

Comparisons with Costa Rica and Spain generate substantially higher potential burdens, exceeding 44,000 and 53,000 deaths, respectively. These figures should not be interpreted as the actual number of deaths that could be prevented through a specific intervention, but rather as counterfactual estimates dependent on the reference used.

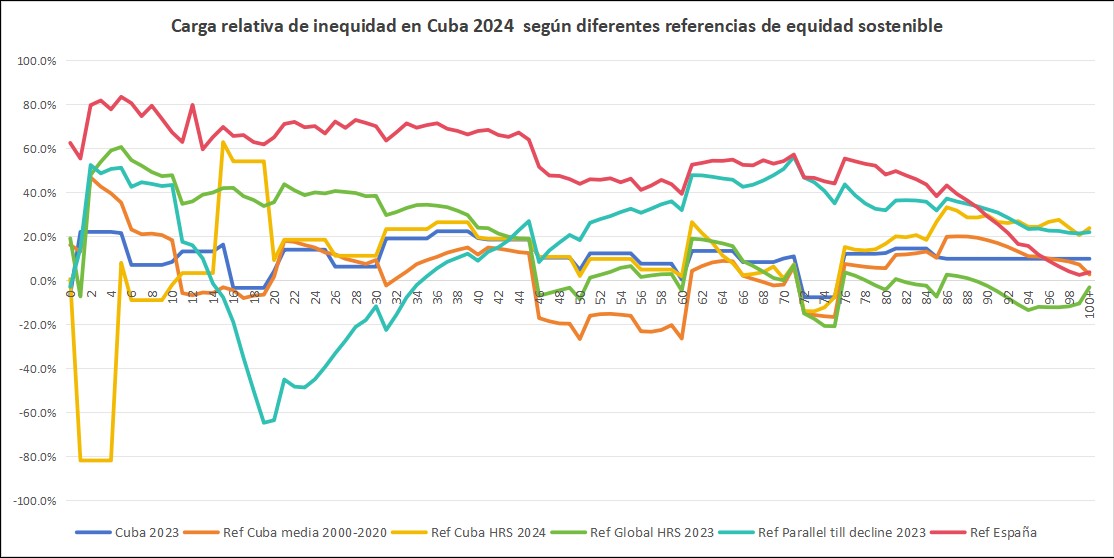
Analysis of the relative burden of inequity (RBI) makes it possible to express these differences as a proportion of observed mortality. In relation to the Cuban period 2000–2019, the estimated RBI for 2024 is around 9.6%. Compared with 2023, it rises to approximately 10.4%. The comparison with Guantánamo reaches 16.4%, while international references generate different values according to the social, economic, and environmental characteristics of each country.

Analysis by age shows that inequity is not distributed evenly. Children and certain younger age groups show particularly sensitive burdens when international references with higher survival are used.
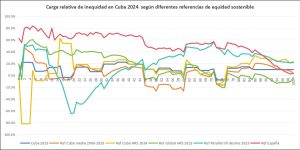
Figure 5. Relative burden of inequity by age and according to different Sustainable Health Equity references

The results suggest that Cuba could benefit from a specific analysis of the factors that allow countries with limited economic resources to maintain better health outcomes. Sri Lanka represents a particularly interesting reference from this perspective, while Guantánamo provides a useful internal reference for identifying potentially replicable territorial practices.

XIII. Years of life lost

Including age in the calculation makes it possible to estimate not only the number of potentially avoidable deaths but also the number of years of life lost.

For 2024, the estimated number of years of life lost associated with the burden of inequity is approximately:

60,000 compared with the Cuban average for 2000–2019.

110,000 compared with Cuba in 2023.

118,000 compared with Guantánamo.

120,000 compared with the Sri Lanka reference.

343,000 compared with Costa Rica.

574,000 compared with Spain.

The differences between these figures demonstrate the importance of carefully selecting the references used. The higher the survival of the population used for comparison, the greater the potential number of years of life lost identified.

This indicator is particularly useful for guiding public policies because it makes it possible to identify where the potential loss of health is concentrated: not only in the number of deaths, but also in deaths occurring at relatively early ages.

XIV. Main patterns of morbidity and mortality

Cardiovascular diseases are the leading cause of death, followed by tumours and respiratory diseases. Cerebrovascular diseases and accidents also account for a significant proportion of mortality.

Infectious diseases have considerably reduced their relative importance compared with previous decades. However, some communicable diseases show worrying trends, including syphilis and certain respiratory infections, hepatitis, and tuberculosis.

From the perspective of years of life lost, tumours are among the main causes, particularly lung, colon, prostate, and breast cancer.

Infant mortality is one of the most sensitive indicators of the current situation. Mortality among children under five may have increased from approximately 6.2 per 1,000 in 2020 to 9.7 per 1,000 in 2024. Two thirds of these deaths occur during the first year of life, and an important proportion are related to perinatal conditions.

Maternal mortality also shows signs of deterioration. In 2024, it was around 33 per 100,000 live births according to the data used in this study, representing an increase compared with the previous year.

Low birth weight has increased from approximately 5% during the two decades preceding the pandemic to around 7–8% in recent years.

Regarding chronic diseases, hypertension, asthma, diabetes, and cerebrovascular disease represent an important burden for the health system, particularly in an increasingly ageing population.

XV. National health system

The Cuban health system maintains a public structure with universal coverage and an extensive primary health care network. This is one of the country’s main assets and should be protected in any cooperation strategy.

Cuba has polyclinics, family medicine practices, hospitals, maternity homes, institutions for older people, and other community-based and specialised services.

The country allocates a high proportion of its public budget to health. However, interpreting health expenditure in US dollars is particularly complex because of the different exchange rates and the difference between nominal values and the real cost of imported goods.

For this reason, rather than relying on a single figure expressed in dollars, it is more useful to analyse the effective capacity of the system to acquire medicines, equipment, fuel, food, and other essential supplies.

Human resources

Until 2020, approximately 400,000 people worked in the Cuban health system. This number may have declined to around 300,000 by 2024.

The number of physicians has also declined substantially, from more than 106,000 in 2020 to approximately 75,000 in 2024. Despite this reduction, Cuba continues to maintain a high physician density by international standards.

The deterioration of salary conditions and economic opportunities in the private sector may be contributing to the movement of professionals from the public health system into other activities or to migration abroad.

The loss of human resources is probably one of the main structural risks to the sustainability of the Cuban health model. Training new professionals takes years and cannot rapidly compensate for the departure of experienced personnel.

Approximately one in six physicians works as a family doctor, integrated into basic health teams and based in the community. The country also has tens of thousands of nursing professionals.

The health system operates through thousands of basic health teams, hundreds of polyclinics and hospitals, and a network of maternal and child, geriatric, and psychopedagogical institutions.

The health information infrastructure, with thousands of units connected to Infomed, represents another important asset for training, scientific communication, and health management.

Activity and coverage of the public health system

In 2024, the National Health System provided more than 100 million consultations, of which approximately 96% were provided through primary health care. Millions of emergency consultations, hundreds of thousands of hospital admissions, and hundreds of thousands of surgical procedures were also recorded.

Vaccination coverage remains one of the main strengths of the system, with coverage close to 98–100% for numerous vaccines included in the national programme.

The national essential medicines list includes around 660 medicines, an important proportion of which are produced domestically. However, economic, energy, productive, and logistical difficulties have significantly reduced their effective availability.

Declining domestic production and imports have resulted in recurrent interruptions in supply. The problem affects not only medicines used in hospitals but also essential treatments for chronic diseases requiring continuity of care.

Informal market for medicines

Insufficient availability of medicines in pharmacies and health facilities has contributed to the expansion of an informal market. Medicines are sometimes brought into the country by travellers and distributed through social networks and personal contacts.

This market may partially compensate for the absence of certain products, but it presents important risks for health and equity. There is not necessarily any guarantee regarding storage conditions, authenticity, expiry dates, or product quality.

Prices observed during the mission show that certain medicines represent an exceptionally high proportion of the incomes of pensioners and public-sector workers.

Medicines Price CUP Proportion of average pension Equivalent in Spain (€)
Paracetamol, 10 tablets 850 24.2% 255
Ibuprofen, 10 tablets 850 24.2% 255
Amoxicillin, 20 tablets 1,700 48.6% 510
Nifedipine, per month 2,250 64.2% 675
Salbutamol, per month 4,000 104.2% 1,200
Enalapril, per month 3,000 85.4% 900
Alprazolam, per month 4,500 128.6% 1,350
Insulin, 300 units/month 12,000 342.8% 3,600

Table 4. Prices of medicines on the informal market, proportion of the average pension, and equivalent values in euros in relation to a salary in Spain

For a person with limited income, common treatments for hypertension, asthma, diabetes, or other chronic diseases may represent a substantial proportion of monthly income. Consequently, purchasing medicines on the informal market may constitute catastrophic health expenditure for some households.

This phenomenon is particularly concerning because it may lead to interruptions in treatment and, consequently, to increased complications, hospitalisations, and avoidable mortality.

XVI. General conclusions

Cuba is experiencing one of the deepest socioeconomic crises of recent decades. The combination of external restrictions, declining productive capacity, inflation, loss of purchasing power, the energy crisis, migration, and population ageing is progressively weakening the capacity of public institutions to guarantee certain basic services.

At the same time, the public system retains important capacities, particularly in health, education, and the training of professionals. The situation should therefore not be interpreted as the disappearance of these capacities, but rather as a process of erosion that may eventually compromise them if resources and productive capacities are not restored.

The development of the private sector represents an important transformation of the Cuban economy. MSMEs have created employment and new sources of income, but so far they have not demonstrated the capacity to replace the redistributive and universal functions historically performed by the State.

The main concern from a public health perspective is that this economic transition may produce increasing segmentation of society between those who have access to foreign currency and those who depend on public salaries or pensions. This inequality may directly translate into differences in food, medicines, transport, energy, housing, and effective access to services.

Recent trends in mortality, life expectancy, infant mortality, low birth weight, and other health indicators constitute warning signals. Data for 2025 and 2026 are still insufficient to establish precisely the magnitude of the deterioration, but they justify strengthening epidemiological and social monitoring.

International cooperation should therefore be directed primarily towards preventing a further loss of essential capacities and protecting the most vulnerable groups.

XVII. Strategic directions for cooperation

The Cuban experience of recent decades raises a broader question: how to preserve achievements in social and health equity in a context of economic restrictions, demographic transition, and ecological crisis.

The response should avoid both an idealisation of the historical Cuban model and an interpretation focused exclusively on its deficiencies. The challenge is to identify which capacities continue to function, which are at risk, and which interventions may contribute to preserving or restoring them.

In this context, four strategic priorities are proposed.

Sustainable energy sovereignty

The first priority should be to move towards greater energy sovereignty based progressively on distributed renewable sources.

Dependence on imported fossil fuels currently represents a systemic vulnerability affecting electricity generation, water supply, hospitals, the preservation of medicines and food, transport, and communications simultaneously.

A strategy based on distributed solar generation, energy storage, and microgrids could initially prioritise health facilities, water systems, rural communities, and other essential services.

The preliminary estimate of approximately 2 kW of solar capacity per inhabitant represents a major investment and would require a specific technical and financial study. Rather than presenting it as an immediate operation, it should be considered as a reference for assessing the scale required for an energy transition.

Part of the country’s public assets, including certain tourism assets, could potentially be assessed as a source of financing for strategic investments, provided that any operation protects the public interest and is evaluated transparently.

Sustainable food sovereignty

The second priority should be the progressive recovery of national capacity to produce healthy and sustainable food.

The increasing dependence on imported food, particularly processed products, creates economic vulnerability, nutritional problems, waste, and logistical dependence at the same time.

The energy transition should be linked to a rural strategy facilitating access to land, water, renewable energy, credit, seeds, and technical assistance for agroecological producers.

Tourism could complement this strategy through rural, ecological, and cultural experiences that generate local income and contribute to financing productive infrastructure.

Fiscal equity and social protection

The third priority should be to strengthen the progressivity of the fiscal system.

In a context of growing inequality between public incomes, remittances, and private economic activities, it is necessary to ensure that people with incomes below a minimum threshold of dignity do not face a fiscal burden that compromises their basic needs.

At the same time, extraordinary incomes and activities with greater capacity to contribute should provide an increasing proportion of resources to finance public goods.

Fiscal policy could also incorporate incentives for activities contributing to the care of people, public health, sustainable food production, renewable energy, the circular economy, and ecosystem protection.

Protection of health, education, and the production of essential medicines

The fourth priority should be to preserve universal and free coverage of essential public services, particularly health and education.

In health, the first objective should be to guarantee the continuity of primary health care and essential treatments for chronic diseases.

The second should be the progressive recovery of national production of essential medicines, including raw materials, formulation, quality control, and distribution systems.

Strengthened national pharmaceutical capacity would not only reduce external dependence but could also allow the development of products of interest to other low- and middle-income countries, transforming certain Cuban capacities into regional or global public goods.

International cooperation could contribute through technology transfer, support for laboratories, joint procurement, quality assurance systems, specialised training, and strengthening supply chains.

XVIII. Final consideration

Cuba is currently facing a critical situation. The combination of external restrictions, internal problems, economic deterioration, population ageing, migration, and the energy crisis is producing a deterioration in living conditions that may compromise some of the social and health achievements accumulated over decades.

At the same time, the country retains important human, institutional, and scientific capacities. The existence of an extensive primary health care network, highly trained professionals, academic institutions, pharmaceutical capacities, and significant historical experience in public health provides a foundation on which action is still possible.

From the perspective of Médecins du Monde, the priority should be to contribute to ensuring that the crisis does not result in an irreversible loss of these capacities and, particularly, in increased inequalities in access to the basic determinants of health.

Cooperation should therefore prioritise interventions with the greatest impact on equity: essential medicines, primary health care, maternal and child health, older people, chronic diseases, mental health, water, energy, and food.

The transition towards greater energy and food sovereignty, accompanied by more progressive taxation and the protection of universal public services, could constitute a strategy capable of simultaneously reducing economic vulnerability, social inequity, and health and environmental risks.

The ultimate objective should not simply be to recover pre-crisis levels, but to build a development model that combines dignity, equity, sovereignty, environmental sustainability, and effective protection of essential public goods.

References
  1. a) Garay, J. (2026). “Cuba’s Health System: From Global Reference in Equity and International Solidarity to Contemporary Crisis.” PEAH – Policies for Equitable Access to Health. Available at: https://www.peah.it/2026/06/16179/
  2. a) Garay, J. (2026). “Cuba: Health Equity, Sustainability and the Limits of a Universal Health System under Prolonged Crisis.” PEAH – Policies for Equitable Access to Health. Available at: https://www.peah.it/2026/06/16179/
  3. b) National Office of Statistics and Information of the Republic of Cuba (ONEI). Statistical Yearbook of Cuba. Latest available editions. Havana: ONEI. Available at: https://www.onei.gob.cu/
  4. c) National Office of Statistics and Information of the Republic of Cuba (ONEI). Studies and publications on population, demography, migration, employment, income, and living conditions. Havana: ONEI. Available at: https://www.onei.gob.cu/
  5. d) Ministry of Public Health of the Republic of Cuba (MINSAP). Statistical Yearbook of Health. Latest available editions. Havana: MINSAP. Available at: https://salud.msp.gob.cu/
  6. e) Pan American Health Organization/World Health Organization (PAHO/WHO). Basic indicators and country profiles: Cuba. Washington, D.C.: PAHO. Available at: https://www.paho.org/es/cuba
  7. f) World Health Organization. Global Health Observatory. Cuba: Health and Health-related Indicators. Geneva: WHO. Available at: https://www.who.int/data/gho
  8. g) United Nations, Department of Economic and Social Affairs, Population Division. World Population Prospects 2024. New York: United Nations. Available at: https://population.un.org/wpp/
  9. h) United Nations Development Programme. Human Development Report 2023/2024: Breaking the Gridlock: Reimagining Cooperation in a Polarized World. New York: UNDP. Available at: https://hdr.undp.org/
  10. i) World Bank. Cuba: data, indicators, and economic and social analysis. Washington, D.C.: World Bank. Available at: https://data.worldbank.org/country/cuba
  11. j) Economic Commission for Latin America and the Caribbean (ECLAC). Economic Survey of Latin America and the Caribbean. Recent editions. Santiago: United Nations. Available at: https://www.cepal.org/
  12. k) Economic Commission for Latin America and the Caribbean (ECLAC). Social Panorama of Latin America and the Caribbean. Recent editions. Santiago: United Nations. Available at: https://www.cepal.org/es/temas/pobreza
  13. l) Food and Agriculture Organization of the United Nations, International Fund for Agricultural Development, United Nations Children’s Fund, World Food Programme, and World Health Organization. The State of Food Security and Nutrition in the World. Recent editions. Rome: United Nations. Available at: https://www.fao.org/publications/sofi/
  14. m) World Health Organization and World Bank. Tracking Universal Health Coverage: Global Monitoring Report. Recent editions. Geneva and Washington, D.C.: WHO and World Bank.
  15. n) Sustainable Health Equity Movement (SHEM). Methodological documents and analyses on sustainable equity, avoidable mortality, and years of life lost. Available at: https://www.sustainablehealthequity.org/
  16. o) Pan American Health Organization. Health in the Americas+: Cuba. Washington, D.C.: PAHO. Available at: https://hia.paho.org/
  17. p) World Health Organization. Access to Medicines and Health Products. Geneva: WHO.
  18. q) World Health Organization. WHO Guideline on Country Pharmaceutical Pricing Policies. Geneva: WHO.
  19. World Health Organization. Medication Without Harm: Global Patient Safety Challenge. Geneva: WHO.
  20. r) World Health Organization. Primary Health Care on the Road to Universal Health Coverage: 2019 Global Monitoring Report. Geneva: WHO.
  21. s) World Health Organization. Operational Framework for Primary Health Care: Transforming Vision into Action. Geneva: WHO and UNICEF.
  22. t) World Health Organization. Social Determinants of Health. Geneva: WHO.
  23. u) World Health Organization. World Report on Ageing and Health. Geneva: WHO, 2015.
  24. v) World Health Organization. Decade of Healthy Ageing 2021–2030. Geneva: WHO.
  25. w) International Organization for Migration. World Migration Report 2024. Geneva: IOM.
  26. x) Médecins du Monde Spain. Institutional documents on humanitarian action, the right to health, equity, and health systems strengthening. Madrid: Médecins du Monde.
  27. y) United Nations. Sustainable Development Goals: Goal 3, Good Health and Well-being. New York: United Nations.
  28. z) World Health Organization. Everybody’s Business: Strengthening Health Systems to Improve Health Outcomes. WHO’s Framework for Action. Geneva: WHO, 2007.
  29. aa) World Health Organization. Monitoring the Building Blocks of Health Systems: A Handbook of Indicators and Their Measurement Strategies. Geneva: WHO, 2010.
Endnotes

[1] https://www.valyter.es/

[2] https://www.sustainablehealthequity.org/

[3] https://www.peah.it/2026/06/16179/

[4] https://www.valyter.es/atlas-de-la-equidad-global

 

News Flash 677: Weekly Snapshot of Public Health Challenges

News Flash Links, as part of the research project PEAH (Policies for Equitable Access to Health), aim to focus on the latest challenges by trade and governments rules to equitable access to health in resource-limited settings

White seabream (Diplodus sargus sargus)

News Flash 677

Weekly Snapshot of Public Health Challenges


Voluntary data submission pilot to advance innovative alternatives to animal testing

Webinar registration: Where Are the PABS Negotiations Heading? Understanding the Africa Group’s Federated Model Sep 7, 2026

Webinar registration: IFIC Forum Discussion on Finance Sep 24, 2026

Webinar registration: From Policy Ambition to System Reality: Improving Access to NCD Medicines in LMICs Sep 25, 2026

Indonesia’s Constitutional Court Restores Safeguards Against Pharmaceutical Patent Evergreening

Amid Ongoing Measles Outbreaks, U.S. Children Remain Vulnerable to Vaccine-Preventable Disease

Respiratory Season Virus Vaccines: Restoring Confidence and Trust

Global initiative launched to improve access to mpox vaccines

Treatment and prevention research on Bundibugyo virus disease must deliver for children, not leave them behind

Feasibility of paediatric schistosomiasis prevention with praziquantel, Madagascar

A Blind Spot in a Humanitarian Catastrophe: Why Yemen’s Jaw Pain Crisis Demands Action by Sami A. Hosain Al-Sakkaf, Ahmed A. Abdulrahman Al-Sakkaf, Akram M. Mohammed Al-Sakkaf

The Road to IHR Reform: How the International Health Regulations were amended to fortify the response to health emergencies

MSF statement: 76th session of the WHO Regional Committee for Africa

HRR832. WE SPEND MORE TIME TRYING TO KEEP TRACK OF INFORMATION THAN USING IT. (Stephen Bezruchka)

Denmark versus UK: which country gets more health for their money?

Measurement of maternal mortality, United Republic of Tanzania

UNICEF Report Underscores Rising Rates of Tech-Facilitated Sexual Abuse Targeting Children

Does aid pay off at home? A new study claims more aid means more exports

UN slashes food aid for occupied West Bank and Gaza amid funding shortfall

The Trump administration cut funds for natural hazards monitoring in Nepal

Nepal’s Flood: Chilling Example of Climate Devastation Facing Developing Countries

Nepal-Tibet flood: this is the cost of not acting in the face of the climate crisis

World Has No Realistic Path to Meet 1.5ºC Warming Target, UN Declares

Occupational heat protection policies

Air pollution across One Health domains

Kenya offers a blueprint for civil society in the ‘America First’ era

Africa Has the Answers to Its Food Security Challenges. What It Needs Is the Architecture to Act on Them

Industrial Aquaculture: better production, better nutrition, better environment, and better life?

Rising Hunger Crisis In Somalia as Millions Go Hungry, WFP Warns

FIAN NEWSLETTER SEPTEMBER 2026 IS OUT! What does the struggle for the right to food look like across different parts of the world?


A Blind Spot in a Humanitarian Catastrophe: Why Yemen’s Jaw Pain Crisis Demands Action

IN A NUTSHELL
Authors’ Note
This brief on temporomandibular disordes (TMD) in Yemen makes three essential contributions: 

Exposes a critical evidence gap - The complete absence of population-based data on TMD in Yemen constitutes a policy failure that perpetuates suffering and wastes scarce resources.

Identifies converging risk factors - The protracted conflict, cultural practice of qat chewing, and healthcare system collapse create a dangerous convergence demanding urgent attention.

Provides a clear, actionable roadmap - Five urgent priorities are outlined: population-based surveillance, mental health integration, culturally appropriate harm reduction, primary care training, and research capacity building. 

The cost of inaction is measured in human suffering; the benefit of action is measured in lives improved

Authors 

Sami A. Hosain Al-Sakkaf¹,²,*

Ahmed A. Abdulrahman Al-Sakkaf¹

Akram M. Mohammed Al-Sakkaf³

¹Faculty of Dentistry, University of Hodeidah, Hodeidah, Yemen

²Center of Tropical Medicine and Epidemiology Studies, University of Hodeidah, Hodeidah, Yemen

³Faculty of Medicine and Health Sciences, University of Aden, Aden, Yemen

*Corresponding Author

Dr. Sami A. Hosain Al-Sakkaf, MSc, PhD

Faculty of Dentistry, University of Hodeidah

Hodeidah, Yemen

ORCID: 0009-0005-0022-7242

Email: Sami.a.h.alsakkaf@gmail.com

A Blind Spot in a Humanitarian Catastrophe: Why Yemen’s Jaw Pain Crisis Demands Action

A Policy Brief


The Problem: A Blind Spot in a Humanitarian Catastrophe

Yemen is collapsing. Twenty-one million people need humanitarian assistance. Less than half of health facilities are functional. The dentist-to-population ratio is half the recommended standard (World Health Organization, 2024). In this landscape of devastation, a silent, invisible, and poorly understood health crisis is unfolding: temporomandibular disorders (TMD).

TMD affects the jaw joint and chewing muscles. It causes chronic pain, difficulty eating, sleep disturbances, and profound psychological distress (Binaljadm et al., 2026). Globally, one in three adults will experience TMD symptoms in their lifetime (Zieliński, Pająk-Zielińska and Ginszt, 2024). But in Yemen? We have absolutely no idea. Not a single population-based study exists (Hajeb et al., 2025). This is not merely an academic gap. It is a policy failure that perpetuates suffering and wastes scarce resources.

FIGURE 1: The TMD Evidence Gap in Yemen – What We Know vs. What We Don’t Know

Comparison of available evidence versus critical knowledge gaps in Yemeni TMD research. Left panel shows the limited findings from 46 convenience-sample studies (1987–2026). Right panel highlights the extensive missing evidence needed for policy and practice. Abbreviations: TMD, temporomandibular disorders; IDP, internally displaced person; OR, odds ratio.

What We Know: A House Built on Sand

A systematic scoping review of all Yemeni research from 1987 to 2026 identified 46 studies. Every single one used convenience samples i.e., clinical patients or university students. None represent the general population (Al-Sakkaf et al., 2026).

Here is what we can say with confidence:

  • Pain is pervasive. In one clinical sample, 82.4% reported pain and 87.2% reported emotional stress (Hajeb et al., 2025).
  • Qat chewing is associated with joint damage. A meta-analysis of 13 observational studies (N=3,526) found an odds ratio of 2.48 (95% CI: 1.20-5.09) for TMD among qat chewers, though with substantial heterogeneity (I²=84.68%) and very low quality evidence (GRADE) (Al-Qadhi et al., 2026).
  • Care-seeking is abysmal. Only 25.7% of symptomatic students sought professional care (Rageh et al., 2025).
  • Treatment evidence is dangerously weak. All treatment studies are small, uncontrolled, and at high risk of bias (Ahmed et al., 2023; Al-hadad et al., 2024; Al-Kibsi and Al-Shamahy, 2024; Sulaiman et al., 2025).
  • Study quality is moderate at best. Mean JBI score was 6.5/9, with 83% using convenience sampling and 76% failing to control for confounding (Al-Sakkaf et al., 2026).

Here is what we cannot say, and this is what should alarm every policymaker:

  • We cannot state the population prevalence of TMD in Yemen.
  • We cannot know whether the burden has changed during the conflict.
  • We cannot determine whether qat chewing causes TMD or whether the association is explained by stress, socioeconomic factors, or other confounders (Al-Qadhi et al., 2026).
  • We have no longitudinal data on progression.
  • Rural and conflict-affected areas are completely unstudied (Al-Sakkaf et al., 2026).

FIGURE 2: The Converging Risk Factors for Temporomandibular Disorders (TMD) in Yemen.

The diagram illustrating the three major risk factor domains converging to create an unmeasured TMD burden in Yemen: protracted conflict, cultural practices (qat chewing), and healthcare system failure. The intersection represents the unknown crisis.

 Why This Matters: The Human and Economic Cost 

TMD is not a minor dental complaint. It is a debilitating condition that impairs nutrition, sleep, mental health, and economic productivity. In a country where food is already scarce and mental health services are virtually non-existent, untreated TMD compounds suffering in ways that are both profound and preventable.

The treatment gap is staggering. Only one in four symptomatic students sought care (Rageh et al., 2025). In rural areas and displacement camps, the gap is almost certainly worse. Barriers include limited awareness, financial constraints, geographic maldistribution of specialists, and a healthcare system in collapse where dental services are deprioritized relative to immediate survival needs (World Health Organization, 2024).

FIGURE 3: The Treatment Gap – Care-Seeking Among Symptomatic Patients.

Care-seeking behaviour among symptomatic dental students in Yemen (n=148). Only 25.7% sought professional care. The lower panel ranks barriers to care by severity, with the most critical barriers in dark red.

Stress is the elephant in the room. Yemenis have endured protracted war, displacement, economic collapse, and loss of livelihood. These are precisely the conditions that exacerbate TMD (Hajeb et al., 2025). Yet mental health support is absent from dental services, and dental care is absent from humanitarian health responses (World Health Organization, 2024).

Qat chewing adds complexity. Qat is culturally embedded and economically significant (Al-Maweri and Halboub, 2026). Stigmatization or prohibition is neither feasible nor helpful. What is needed is culturally appropriate harm reduction that respects local practices while addressing potential health impacts. This requires research, dialogue, and community engagement, not moral posturing.

FIGURE 4: The Historical Contradiction – Qat and TMD Evidence Over Time (1987–2026).

Timeline showing the evolution of evidence on qat chewing and TMD in Yemen. Colour-coded markers indicate evidence type: blue (clinical examination), green (imaging), orange (clinical trial), purple (systematic review). The yellow caution box highlights that all studies are cross-sectional, so causality remains unproven.

Abbreviations: TMJ, temporomandibular Joint; TMD, temporomandibular disorders; OR, odds ratio; CI, confidence interval; MRI, magnetic resonance imaging; CBCT, cone beam computed tomography; PR, prevalence ratio; ABI, autologous blood injection.

The Historical Contradiction: A Warning Sign

The earliest study on qat and oral health in Yemen, conducted by Hill and Gibson (1987), found no detrimental effects. Modern evidence from MRI and CBCT studies tells a dramatically different story: significantly higher rates of osteoarthritis (P=0.003), joint effusion (P=0.002), osteophytes (PR 2.26, 95% CI: 1.27-4.02), and cysts (PR 9.75, 95% CI: 2.08-45.7) in qat chewers (Almashraqi et al., 2018; Almashraqi et al., 2020).

Why the contradiction? Methodological improvements (clinical examination versus advanced imaging), secular changes in qat use over four decades, the massive increase in psychosocial stress due to conflict, and the inclusion of both sexes in later studies (Almashraqi et al., 2018; Almashraqi et al., 2020). But the cross-sectional design of all studies means causality remains unproven (Al-Qadhi et al., 2026). This is not a reason for inaction. It is a reason for urgent, high-quality research.

FIGURE 5: Yemen vs. Global TMD Evidence – A Comparison

Comparison of global TMD evidence standards (left) with the current Yemeni evidence base (right). Global estimates are derived from meta-analyses (Zieliński, Pająk-Zielińska and Ginszt, 2024; Alqutaibi et al., 2025). Yemen data are from convenience samples only. The red/grey shading indicates critical missing evidence.

Abbreviations: TMD, temporomandibular disorders; OR, odds ratio; RCT, randomised controlled trial; CI, confidence interval.

Five Urgent Priorities for Action

FIGURE 6: Five Urgent Priorities – The Way Forward

Staircase infographic showing the five priority actions required to address the TMD crisis in Yemen. Each step includes a key message and is colour-coded by priority domain.

Abbreviations: TMD, temporomandibular disorders; DC/TMD, Diagnostic Criteria for Temporomandibular Disorders.

  • Establish Population-Based Surveillance – Now

This is non-negotiable. Without prevalence data, there is no basis for resource allocation, service planning, or policy making (Al-Sakkaf et al., 2026). Surveillance should use the internationally validated DC/TMD diagnostic criteria (Schiffman et al., 2014). Where security permits, this can be integrated into existing health information systems or humanitarian assessments. We cannot manage what we do not measure.

  • Integrate Mental Health Support into Dental Services

With 87.2% of TMD patients reporting emotional stress (Hajeb et al., 2025), dental providers must be trained to assess psychological factors and make appropriate referrals. Where mental health services are unavailable, brief psychosocial support can be integrated into dental care. This is not optional. It is essential.

  • Develop Culturally Appropriate Harm Reduction for Qat Chewing

Prohibition is not the answer. Harm reduction is. Interventions should focus on reducing chewing duration, promoting bilateral chewing, and raising awareness of potential risks. Community leaders and religious scholars must be engaged. Research is needed to test the effectiveness of such approaches.

  • Train Primary Care Providers in Basic TMD Assessment

Specialists are concentrated in urban areas and are scarce. Primary care providers including general dentists and community health workers, can be trained to recognize TMD, provide conservative management, and make appropriate referrals. This is feasible even in resource-constrained settings. The current reality is alarming: only 41.5% of dentists in Aden accurately defined centric relation, and 68% of public-sector dentists lacked articulators (Elsheikh et al., 2025). Only 1.1% of general dentists reported ability to independently manage suspected stomatognathic movement disorder cases (Jamali et al., 2026). This must change.

  • Build Research Capacity Through International Collaboration

Yemeni researchers face extraordinary challenges: security risks, limited infrastructure, and brain drain (World Health Organization, 2024). International partnerships can provide technical support, training, and mentorship while ensuring that research is locally led and culturally appropriate. Remote research methods should be explored where field work is not feasible. The global health community cannot look away.

FIGURE 7: The Human Cost – TMD Impacts on Daily Life

Human-centred infographic illustrating the cascading impacts of untreated TMD on an individual’s life. The jaw is highlighted In red, with radiating effects on pain, nutrition, sleep, mental health, productivity, and social wellbeing.

Abbreviations: TMD, temporomandibular disorders.

The Cost of Inaction: Predictable and Preventable

The consequences of continued inaction are not speculative. They are predictable:

  • Untreated TMD will cause ongoing suffering, impaired nutrition, and reduced productivity.
  • Health resources will continue to be allocated without evidence.
  • The treatment gap will widen.
  • Yemen will remain a blind spot in the global understanding of TMD in conflict settings.

The cost of action is modest. Integrating TMD assessment into existing health surveys requires minimal additional resources. Training primary care providers can be done through existing continuing education mechanisms. International research partnerships often bring their own funding.

What is lacking is not resources. What is lacking is awareness and prioritization.

FIGURE 8: Yemen – A Blind Spot on the Global TMD Map

World map showing TMD data availability globally. Countries with extensive research are shaded dark blue; those with limited or no data are grey. Yemen is highlighted in red with a question mark, indicating the complete absence of population-based TMD data.

Abbreviations: TMD, temporomandibular disorders.

A Call to Action: Who Must Do What

To the Yemeni Ministry of  Health and Population:

  • Include TMD surveillance in national health information systems.
  • Integrate dental and mental health services.
  • Support training for primary care providers.

To international donors and humanitarian agencies:

  • Recognize oral health as part of essential health services.
  • Fund population-based research.
  • Support mental health integration.
  • Include dental care in humanitarian health packages.

To researchers and academic institutions:

  • Partner with Yemeni investigators.
  • Support capacity building.
  • Publish and disseminate findings.
  • Advocate for policy change.

To the global health community:

  • Recognize that conflict-affected populations face unique health challenges that are poorly understood.
  • Support research that can inform evidence-based responses.
  • Ensure that oral health is not neglected in humanitarian settings.

FIGURE 9: The Research-to-Policy Pipeline

Horizontal pipeline showing the pathway from research gap identification to policy implementation. Only Stage 1 (Research Gap Identified) has been achieved. Stages 2–7 remain incomplete, highlighting the urgent need for action.

Abbreviations: TMD, temporomandibular disorders; DC/TMD, Diagnostic Criteria for Temporomandibular Disorders.

Conclusion: The Evidence Is Absent, but the Need Is Not

Yemen’s conflict has created a convergence of risk factors for TMD: widespread stress, disrupted healthcare, and cultural practices that may affect joint health. Yet the evidence base is critically insufficient. We cannot manage what we do not measure. We cannot treat what we do not recognize. We cannot plan without data.

The primary contribution of this review is not what it reveals but what it exposes: a near complete absence of population-based evidence. This is not merely an academic gap. It is a policy failure that perpetuates suffering and wastes scarce resources.

The way forward is clear. Establish surveillance. Integrate services. Train providers. Build capacity. The cost of inaction is measured in human suffering. The benefit of action is measured in lives improved.

The evidence is absent, but the need is not. It is time to act.

FIGURE 10: Summary –  Key Messages and Call to Action

Four-quadrant summary infographic consolidating the key messages of this policy brief. The central call to action emphasises that the evidence is absent but the need is not. Contact information is provided for the corresponding author.

Abbreviations: TMD, temporomandibular disorders; OR, odds ratio; CI, confidence interval.

Acknowledgements

The authors extend their sincere gratitude to all researchers whose work formed the foundation of the scoping review informing this policy brief. The authors gratefully acknowledge the insightful contributions of Prof. Dr. Mahmood Md. Mohsen Al-Sakkaf, Genetic-Epidemiologist at the Faculty of Medicine and Health Sciences, University of Aden, Yemen, for his expert guidance and critical appraisal of the evidence synthesis. The authors also thank their respective institutions for providing the academic environment and support necessary for this work.

Conflicts of Interest

The authors declare that they have no conflicts of interest.

Funding

None. This research received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.

Ethical Considerations

This policy brief is based on a systematic scoping review of published literature and did not involve primary data collection from human participants. All data were derived from previously published, peer-reviewed studies; no individual patient data were accessed or analyzed. Ethical approval was therefore not required. The authors adhered to standard scientific integrity principles, including transparency, accuracy in data reporting, and proper attribution of original sources. This work was conducted in accordance with the Declaration of Helsinki principles regarding research integrity and the responsible conduct of research.

Data Availability

All data are derived from published studies and reports cited in the reference list. No primary data were collected. The full scoping review is available from the corresponding author upon reasonable request.


References

Ahmed, M.M.S., Shi, D., Al-Somairi, M.A.A., Alhashimi, N., Almashraqi, A.A., Musa, M. et al. (2023) ‘Three dimensional evaluation of the skeletal and temporomandibular joint changes following stabilization splint therapy’, BMC Oral Health, 23, p. 18. doi:10.1186/s12903-023-02720-w.

Al-hadad, S.A., Ahmed, M.M.S., Zhao, Y., Wang, L., Hu, W., Li, C. et al. (2024) ‘Skeletal, dentoalveolar and soft tissue changes after stabilization splint treatment for patients with temporomandibular joint disorders’, BMC Oral Health, 24, p. 479. doi:10.1186/s12903-024-04260-3.

Al-Kibsi, T.A.M. and Al-Shamahy, H.A. (2024) ‘Effectiveness of Butorphanol Intra Articular Injection in Signs and Symptoms of Internal Disorders of the Temporomandibular Joint’, Sana’a University Journal of Medicine and Health Sciences, 18(1), pp. 11-16. doi:10.59628/jchm.v18i1.587.

Al-Maweri, S.A. and Halboub, E.S. (2026) ‘Khat (Catha edulis) Chewing and Oral Health’, in Prabhu, S.R., Warnakulasuriya, S. and Bhardwaj, S. (eds.) Lifestyle in Oral Health and Disease. Cham: Springer, pp. 97-110. doi:10.1007/978-3-032-05888-1_8.

Al-Qadhi, G., Al-Wesabi, M., Almashraqi, A.A., Ali, K., Almeslet, A.S., Al-Maweri, A.A. and Al-Maweri, S.A. (2026) ‘Association between khat chewing and temporomandibular disorders: a systematic review and meta-analysis of observational studies’, BMC Oral Health, 26(1), p. 433. doi:10.1186/s12903-026-07789-7.

Al-Sakkaf SAH, Al-Sakkaf AAA, Al-Sakkaf AMM. Beyond the War: Mapping the Hidden Burden of Temporomandibular Disorders in Conflict‑Affected Yemen: A Scoping Review and Research Agenda [Preprint]. ResearchGate; 2026 Aug [cited 2026 Aug 26]. Available from: https://www.researchgate.net/publication/413623013_Beyond_the_War_Mapping_the_Hidden_Burden_of_Temporomandibular_Disorders_in_Conflict-Affected_Yemen_A_Scoping_Review_and_Research_Agenda

Almashraqi, A.A., Ahmed, E.A., Mohamed, N.S. and Halboub, E.S. (2018) ‘An MRI evaluation of the effects of qat chewing habit on the temporomandibular joint’, Oral Surgery, Oral Medicine, Oral Pathology and Oral Radiology, 126(3), pp. 272-282.e2. doi:10.1016/j.oooo.2018.05.005.

Almashraqi, A.A., Halboub, E.S., Al-Maweri, S.A., Barngkgei, I., Al-wesabi, M.A., Al-kamel, A. et al. (2020) ‘Cone Beam Computed Tomography Findings in Temporomandibular Joint of Chronic Qat Chewers: Dimensional and Osteoarthritic Changes’, Journal of Oral Rehabilitation, 47(12), pp. 1538-1549. doi:10.1111/joor.13092.

Binaljadm, T.M., Al-Gabri, R.S., Saker, S., AboAlrejal, H.O., Saeed, M.H. and Alqutaibi, A.Y. (2026) ‘Temporomandibular Disorders Diagnosis: Current Challenges and the Promising Role of Artificial Intelligence’, European Journal of Dentistry. doi:10.1055/s-0046-1816081.

Elsheikh, N.M.A., Farhan, H.M.Q., Ali, H.A.A. et al. (2025) ‘Knowledge and Perception of Occlusion among Dentists in Aden, Yemen’, Yemeni Journal of Medical Sciences, 19(11). doi:10.20428/yjms.v19i11.3341.

Hajeb, R.M., Abdulghani, M.A.M., Al-wesabi, M.A. and Al-Maweri, S.A. (2025) ‘Exploring the Risk Factors Associated with Temporomandibular Disorders: A Cross-Sectional Study Among a Sample of Yemeni Patients’, Malaysian Journal of Public Health Medicine, 25(2), pp. 201-210. doi:10.37268/mjphm/vol.25/no.2/art.3315.

Hill, C.M. and Gibson, A. (1987) ‘The oral and dental effects of q’at chewing’, Oral Surgery, Oral Medicine, Oral Pathology, 63(4), pp. 433-436. doi:10.1016/0030-4220(87)90255-6.

Jamali, O.M., Jamali, R., Al Riachi, M., Al-sharjabi, M., Abu sanad, K., Hussein, B. et al. (2026) ‘Are dental practitioners prepared to recognize stomatognathic movement disorders?’, BDJ Open, 12, p. 75. doi:10.1038/s41405-026-00470-9.

Rageh, O.A., Al-Yafeai, E., Al-Malahi, H. et al. (2025) ‘Prevalence of Temporomandibular Joint Disorders (TMD) Among Dental Students in Yemeni Universities’, Yemeni Journal of Medical Sciences, 19(4). doi:10.20428/yjms.v19i4.2860.

Schiffman, E., Ohrbach, R., Truelove, E. et al. (2014) ‘Diagnostic Criteria for Temporomandibular Disorders (DC/TMD) for Clinical and Research Applications’, Journal of Oral and Facial Pain and Headache, 28(1), pp. 6-27. doi:10.11607/jop.1151.

Sulaiman, A.S.A., Abbas, A.K.M.A., Abdul Majid, A.L.A., Al-Rohmi, F.M.A., Al-Muntaser, A.Q.H., Al-Moyed, K.A. et al. (2025) ‘Effects of Low Level Laser in the Treatment of Myofascial Pain Dysfunction Temporomandibular Joint’, Universal Journal of Pharmaceutical Research, 10(2). doi:10.22270/ujpr.v10i2.1314.

World Health Organization (2024) Yemen Health Cluster Bulletin. Available at: https://www.emro.who.int/yemen/yemen-infocus/health-cluster-bulletin.html  (Accessed: 15 August 2026).

Zieliński, G., Pająk-Zielińska, B. and Ginszt, M. (2024) ‘A Meta-Analysis of the Global Prevalence of Temporomandibular Disorders’, Journal of Clinical Medicine, 13, p. 1365. doi:10.3390/jcm13051365.


About This Brief

This policy brief is based on a systematic scoping review of 46 Yemeni primary research studies on temporomandibular disorders conducted between 1987 and 2026. The review followed PRISMA ScR guidelines and included quality appraisal using JBI tools and Cochrane RoB 2.0. The full review is available from the authors upon request.

Key Messages

  1. Not a single population-based study on TMD exists in Yemen (Al-Sakkaf et al., 2026)
  2. All available evidence comes from convenience samples and cannot provide prevalence estimates (Al-Sakkaf et al., 2026)
  3. High stress (87.2%) and low care-seeking (25.7%) are consistently observed (Hajeb et al., 2025; Rageh et al., 2025)
  4. Qat chewing shows cross-sectional associations (OR 2.48; 95% CI: 1.20-5.09) but causality is unproven (Al-Qadhi et al., 2026)
  5. Five urgent priorities are identified: surveillance, mental health integration, harm reduction, provider training, and research capacity building
About the Authors and Their Contributions

All authors contributed equally to the conceptualization, scope definition, target audience identification, and systematic investigation. They collectively conducted the literature review and synthesis of peer-reviewed studies from Yemen, WHO reports, and international literature to support this policy brief. All authors reviewed and approved the final manuscript.

Dr. Sami A. Hosain Al-Sakkaf, MSc, PhD

Orthodontist & TMJ Specialist | 25+ years in clinical practice, education, and research | Faculty of Dentistry, University of Hodeidah, Yemen | Lead Author, Temporomandibular Disorders: A Comprehensive Guide for Yemeni Dental Students (in press) and the TMD Scoping Review | Research interests: TMD, craniofacial growth, and orthodontic care in resource-limited settings | Corresponding author.

ORCID: 0009-0005-0022-7242

Email: Sami.a.h.alsakkaf@gmail.com

Dr. Ahmed A. Abdulrahman Al-Sakkaf, BDS

Dentist & Oral Health Researcher | Faculty of Dentistry, University of Hodeidah, Yemen | 10+ years in clinical dentistry, education, and research | Co-Author of the TMD Scoping Review and textbook | Research interests: oral health epidemiology, TMD, and dental education in conflict-affected settings.

ORCID: 0009-0009-9914-6635

Email: Ahmed.a.a.AlSakkaf@gmail.com

Dr. Akram M. Mohammed Al-Sakkaf, MBChB, MPH

Physician, Public Health & Implementation Research Specialist | WHO-TDR Fellow | University of Aden | 15+ years in public health, research, and health programming | Co-Author of the TMD Scoping Review and textbook | Research interests: health systems strengthening, implementation science, and equitable service delivery in humanitarian settings.

ORCID: 0000-0003-4709-4596

Email: Akram.m.alsakkaf@gmail.com


News Flash 676: Weekly Snapshot of Public Health Challenges

News Flash Links, as part of the research project PEAH (Policies for Equitable Access to Health), aim to focus on the latest challenges by trade and governments rules to equitable access to health in resource-limited settings

Common octopus (Octopus vulgaris)

News Flash 676

Weekly Snapshot of Public Health Challenges


World Humanitarian Day: Why humanitarian settings need more research, not less

Reforming global health for an age of mistrust, fragmentation and overlapping crises

Measuring the composition and availability of human resources for health by sex in 204 countries and territories, 1990–2023, and workforce gaps for universal health coverage: a systematic analysis for the Global Burden of Disease Study 2023

AI Philanthropy Should Buy the Breakthroughs Markets Won’t

IFIC Canada Webinar: Digitally Enabled Integrated Care: Ambition, Adoption, and Scale Sep 8, 2026

IFIC Scotland Webinar: Community Hospitals across the Globe Sep 16, 2026

Urgent health update: Consequences of war on Gaza, the West Bank/East Jerusalem, and Lebanon – August 15, 2026

SA and Zambia’s HIV shot dilemma: Demand versus supply

Ebola Outbreak Becomes Deadliest in DR Congo’s History

Other health emergencies must not be neglected in eastern DRC

World Mental Health Day 2026: Announcing This Year’s Theme

Iodine Network: 2025 annual report

Construction and Practice of the County Integrated Healthcare System in China: A Case Study of Shaxian, Sanming

HRR830. WOMEN’S RIGHTS: POLICY WITHOUT POLITICAL WILL IS NOT JUST INEFFECTIVE –IT IS VIOLENCE. # (Sulakshi Ram)

Americas: Regional Conference on Population and Development must uphold international commitments on gender equality

Ceuta’s border crisis is about geopolitics, not just migration

Indigenous communities file complaint in Norway against Statkraft under Transparency Act – Initiative for Transnational Justice – ProDESC

Sign the Petition – Norway: Save the Pilmaiquén

USAID fallout: In Nepal, when the aid workers stopped coming, the women and babies started dying

Nearly 4 million Afghan children ‘acutely malnourished’

Aid shortages and fears of starvation as Indonesia reels from deadly earthquake

Colombia earthquake: UN ramps up aid for 100,000 people

As Funding Shrinks, Africa’s SRHR Movement Vows Not to Retreat

‘Syringes on beaches’ as hospital waste goes unchecked

No Limits: Ryan Eddowes on Disability, Wildlife & Conservation

What to expect at this year’s desertification COP

As Mongolia Hosts COP17, Pastoralists Demand Space to Move, Survive and Restore

Indigenous Peoples Call for Meaningful Influence in Climate Discussions — Nia Tero

UN plastic treaty is going backwards, experts say

Register: BlueAdapt final conference: Climate change & health: building resilience and reducing risks in coastal environments 22 September, 2026


News Flash 675: Weekly Snapshot of Public Health Challenges

News Flash Links, as part of the research project PEAH (Policies for Equitable Access to Health), aim to focus on the latest challenges by trade and governments rules to equitable access to health in resource-limited settings

Flying gurnard (Dactylopterus volitans)

News Flash 675

Weekly Snapshot of Public Health Challenges


Book: India’s Undernutrition and Human Capital – Addressing the Roots by Veena S Rao

Meeting registration: IFIC Forum Discussion on Health in Context Sep 9, 2026

EPN Forum 2026: Sustainable and Resilient Health Systems for Last-Mile Access in Africa 5th – 9th October 2026

MMI participation at the WHO Civil Society Dialogues on Health Financing

UN tax talks reach critical stage as global south pushes for fairer rules

Ebola response concerns, Tigray war warnings, and Gaza’s ceasefire mirage

Haiti: MSF forced once again to suspend operations at the Isaïe Jeanty Maternity hospital amid violence

Whose fears count? Legitimacy, trust and viral outbreak responses after COVID-19

People’s Health Dispatch  Bulletin #122: Ebola outbreak swells into largest ever in DRC

Africa CDC and WHO call for urgent, community-led action to contain Ebola in the DRC

Alarming Ebola Spread Raises Question of Viral Mutation

MSF launches dengue project in Tegucigalpa, Honduras

Mosquitoes are spreading dangerous dengue in US states. Here’s where to watch out

Pakistan’s HIV Surge Exposes Infection Control Failures at Health Facilities

Mixed feelings: Unintended consequences of HIV outreach care in Zimbabwe

Stretching Mpox Vaccine Supply: Madagascar’s Fractional Dosing and the Case for Doing It Better

Re-emergence of vaccine-preventable diseases in the post-elimination era

A model for the epidemiological impact of tuberculosis policy options

Foodborne Illnesses Are Skyrocketing: 6 to Know About

A new chapter for African medical innovation

Zero deaths on paper, fear in reality: In spite of Goa achievement, rabies still haunts India

HRR829. LIBERAL DEMOCRACY: IT IS TIME TO ACKNOWLEDGE THAT THIS HISTORICAL PROCESS HAS RUN ITS COURSE AND IS PRODUCING PERVERSE EFFECTS. (Boaventura de Sousa Santos)

Hiroshima Day Appeal 2026

Palestinian Children Deserve Education, not Ethnic Cleansing

15 August 2026: Five years of Taliban oppression, repression and pervasive impunity for crimes against women and girls

Zambia: stalled reforms risk reversing human rights gains

Lebanon: Abolition of death penalty a landmark victory affirming justice must be rooted in human rights

Sudan’s war threatens an ‘entire generation’s’ future, UN warns

The World Bank Is Pouring Billions of Dollars into Large-scale Factory Farms

Where Some See Waste, Others See Opportunity: Young Sierra Leoneans Fight Against Electronic Waste, Plastic Pollution

Early Warnings: Government Knowledge of Climate Change and Legal Responsibility for Climate Harm


News Flash 674: Weekly Snapshot of Public Health Challenges

News Flash Links, as part of the research project PEAH (Policies for Equitable Access to Health), aim to focus on the latest challenges by trade and governments rules to equitable access to health in resource-limited settings

Scorpionfish (Scorpaena)

News Flash 674

Weekly Snapshot of Public Health Challenges


Rethinking Humanitarianism | Error and trial: What really makes the humanitarian system change?

From mobilisation to development impact: making private finance work for development

Where the Trump Administration’s Global Health Agreements Stand

Hijacking The Chronic Disease Epidemic

Countries urged to strengthen breastfeeding support and health systems to give every child a healthy start in life

Preparation of an emergency-ready health workforce; a call for papers

Ebola Treatment Centre Opens, Clinical Trials Start in DR Congo

Fear and Fatigue Grip Congo’s Health Workers as Ebola Response Crumbles

Ebola outbreak: MSF statement on WHO Director General’s high-level visit to DRC

EXCLUSIVE: Here is the ‘Final Text’ of UN Political Declaration on Pandemics – Although its Adoption is Far From Guaranteed

Why Pandemic Preparedness Is Failing: Inequality as the Missing Link

World AIDS Conference to the World: We Have a Problem!

Zimbabweans Fleeing Xenophobia in South Africa Battle to Get HIV Medicine Back Home

#Aids2026: Three HIV announcements South Africa made in Rio

AIDS 2026: Navigating HIV Care in a New Funding Reality

Pricing pivotal as HIV drug advances offer ‘choice’

Identification of unvaccinated children, Madagascar

U.S. Disease Tracker Launches to Strengthen Monitoring of Vaccine-Preventable Diseases

Scientists Warn Drug-Resistant Malaria Mutation Is Spreading Across Lake Victoria Basin

Expedited research and approval of medicines for drug-resistant bacterial infections in children

Bridging the Equity Gap: Financing Indonesia’s National Stroke Strategy

Building African evidence for cancer care

Tracking the real-world impacts of US foreign aid cuts

Female Genital Mutilation: Winning the Argument, Losing the Funding

HRR828. GLOBAL HEALTH IS IN THE MIDST OF A PROFOUND STRUCTURAL CRISIS

Safer and more transparent AI

How to Reduce Child Poverty: What Two Decades of Progress in Peru Can Tell the World

Food Shortages and Cholera Deepen Sudan’s Humanitarian Crisis

The Right to Food and Nutrition, support for small-scale peasants, and protection of communities’ lands in Burkina Faso must be a reality

Health Impacts of Natural Gas Flaring: A Literature Review of Nigeria, Iraq, and Brazil